What is Preprosthetic Surgery?
The restoration of tooth loss is one of the fundamental topics of dentistry. However, for a prosthesis to perform its function, it depends on the anatomical quality of the tissue it will rest upon. Prolonged toothlessness can lead to the resorption of the jawbone or sagging of soft tissues. Sharp remnants, cavities, or the proximity of the lip/tongue attachments (frenulum) to the area where the prosthesis will sit makes it difficult for the prosthesis to remain stable in the mouth. Preprosthetic surgery includes preparatory interventions aimed at eliminating these challenging physiological barriers to support the carrying and retention of the prosthesis. With these procedures, the prepared prosthesis transmits chewing forces to the jaw in a balanced manner without irritating the oral mucosa.
At the Avrupadent clinics in Izmir, pre-prosthetic surgical procedures are carried out with a coordinated approach between the prosthetic and surgical branches. The reconstruction of jaw anatomy helps to prevent potential trauma and pain complaints associated with prosthesis use. The operations not only remove existing tissue excesses or bone sharpness but also enrich the area using support materials in regions where bone volume is insufficient. These medical arrangements ensure that the patient can maintain chewing and speaking functions at an ideal level in harmony with the prosthesis.
In Which Cases is Pre-Prosthetic Surgery Applied?
The performance of a prosthesis depends on its compatibility with the underlying tissue. If the jawbone is irregular, the delicate gum tissue is compressed against these bone sharpness areas when the prosthesis exerts pressure, causing pain. The primary anatomical conditions for which a surgical adjustment decision is made before prosthesis production in patients starting at the clinic are:
| Clinical Condition | Need for Surgical Intervention |
|---|---|
| Irregular Alveolar Crests | Healing with irregular bony undercuts following tooth extractions, creating pressure areas underneath the prosthesis. |
| Bony Exostoses (Tori) | Physiological bony enlargements found on the hard palate or on the tongue side of the lower jaw that interfere with prosthesis seating. |
| Soft Tissue Enlargements | Wrinkles, movable excess mucosal layers (epulis fissuratum) caused by irritating old incompatible prostheses. |
| Short Muscle Attachments | Keeping the frena of the lips, cheeks, or tongue very close to the gum line, displacing the prosthesis during speech. |
What Are Preprothetic Surgical Procedures?
The nature of the procedure to be performed is determined based on the condition of the tissue where the patient will carry the prosthesis. Correcting the sharp edges remaining in the jawbone immediately after tooth extraction is often the first step taken. In cases where the bone structure is appropriate but the gum contour is irregular, only soft tissue excisions (cuts) are planned. When the area where the oral mucosa meets the inner surface of the lip and cheek is tight, there is no remaining boundary for the retention of removable prostheses. Vestibuloplasty procedures allow for better placement of the prosthesis between the cheek and the bone by pulling this area lower.
On the other hand, long-term use of poorly fitting prostheses causes the tissues to react. The gums layer themselves to protect against the areas where the prosthesis impacts. The removal of these moving and inflamed mucosal layers through cautery, laser, or classic surgical methods is a medical necessity for the new prosthesis to press against healthy mucosa.
How is Pre-prosthetic Surgery Planned?
In İzmir Avrupadent, this design is crafted with a “restoration-focused” perspective. Before the surgical procedure begins, the doctor establishes the limits, thickness, and lip support of the final prosthesis that the patient will use, either in a virtual environment or on models. The surgeon maps the bone defects or movable tissues that interfere with the limits of this prosthesis. The portion of the bone from which tissue will be removed is predefined within this planning.
During the planning phase, the nerve pathways under the mandible and the anatomical spaces in the upper jaw are taken into account within safety limits. In areas where the bone structurally requires support, adding tissue (grafting) to support the profile instead of reducing it can also be part of the surgical schedule. This meticulous infrastructure work is crucial for the patient to comfortably use their prosthesis.
Who Can Be Suitable for Preprosthetic Surgery?These procedures are considered for adult individuals with dental deficiencies who are expected to use prostheses but whose oral anatomy does not allow for proper prosthesis retention, those who experience constant movement of their existing prosthesis during speech or eating, and those with a medical profile that indicates suitability for local surgical procedures.
As long as the systemic health values are at an ideal level, age is not a limiting factor for this surgery. On the contrary, since the need for a complete (dental plate) prosthesis is often more common in older age groups, preprosthetic interventions are frequently implemented to support the chewing quality of patients in this age range. The patient is prepared structurally for the new prosthesis.
For individuals with diabetes (sugar disease), cardiovascular problems, or bleeding profile irregularities, it is recommended to control medical findings in consultation with their healthcare provider. Individuals whose medical values are stabilized can safely participate in these tissue modification procedures, provided they follow the doctor’s recommendations.
How is an assessment made before Preprosthetic Surgery?The clinical assessment phase; involves analyzing the systemic discomforts of the patient and the medication history, identifying bone protrusions during manual examination, measuring the thickness of the tissues where the prosthesis will sit, and thoroughly examining the jawbone topography with radiographic films.Successful prosthetic fabrication is possible with a thorough physical assessment. If the patient has an old prosthesis, the doctor examines the areas of tissue damage created by that prosthesis. Traumatic ulcers or mucosal layers caused by the prosthesis are identified. Areas with rough surfaces on the bone and sharp alveolar edges (of the jaw crest) that could cause pain under the prosthesis are mapped.
The extent to which the patient’s lip and cheek muscles (facial expressions) retract the connective tissue is tested while speaking. This retraction force helps to determine whether the short frenula (attachments) tied to the gum line will displace the prosthesis. In patients using blood-thinning agents, it is essential to establish a consultation with the physician before the operation to ensure the bleeding situation is secured, which forms the medical aspect of the process.
What Steps Are Taken in Preprosthetic Surgical Process?
The steps taken to support tissue repair and arrange anatomical boundaries are carried out successively while respecting surgical principles. The steps followed in a basic intervention are as follows:
\t- • Anesthesia Application: The numbing of the nerve fibers surrounding the operative area with local agents to ensure clinical comfort.
\t
- • Tissue Incision and Separation: The removal of excess tissues using a scalpel or laser or the gentle separation of the mucosa like a delicate flap to reach the underlying bone.
\t
- • Bone Shaping (Alveoloplasty): The smoothing and rounding of irregular bone edges by filing with special surgical burs.
- ▪ Washing and Stitching (Suturing): Closing the area of work by stitching it in a way that will be compatible with the new prosthetic borders after washing the tissue with physiological serums.
What Should Be Considered Before Preprosthetic Surgery?
Factors that patients should pay attention to before the procedure: attending the appointment at the scheduled time with maintained oral hygiene, adjusting medication doses under the medical doctor’s knowledge, ensuring that previously damaged prosthetics are not used for a few days prior to the procedure to allow the tissue to rest, and arriving at the clinic in a fasting state to balance stress levels.Keeping the microbial load of the working area at a minimum during surgical interventions prevents complications that may arise during the healing period. The patient should carefully clean their teeth and gums before the operation, and if recommended, should use antiseptic mouthwashes. Prescribed blood pressure medications or diabetes pills should continue to be taken at routine times.
Due to the procedure being performed under local anesthesia, it is recommended that the patient arrives for the appointment in a slightly fasting and rested state to keep the hospital’s blood sugar and blood pressure levels stable. If the use of tobacco that slows down cellular repair is present, limiting this habit before the day of the operation supports the repair process from a clinical perspective.
What Should Be Considered After Preprosthetic Surgery?
Post-Intervention Considerations; to support tissue healing, a soft diet should be followed in the first days, cold compresses applied intermittently from the cheek area to limit swelling, avoiding the consumption of tobacco products for a certain period, and regular use of prescribed medications.After surgical procedures, slight swelling in the cheek or lip area and tiny leaks observed inside the mouth are a natural response of cellular repair. Applying ice compresses in the first 24 hours significantly limits this swelling. It is advisable to swallow to move the area in the first days, as chewing, drinking with a straw, or forcefully gargling may disrupt the clot formed in the wound area.
After the operation, if the physician has not adapted the inside of the old prosthesis with a soft lining material, it may be advised that the patient avoid wearing the old prosthesis for a few days to prevent pressure on the sutured area. Acidic, hot, and spicy foods should be removed from the menu as they may irritate the healing mucosa. The use of tobacco should be restricted until the wound has closed, as it can impair tissue blood flow.
Which Prosthetic Treatments Are Evaluated Before Preprosthetic Surgery?
The correction of tissue surface is often planned in wide surface restorations that derive their foundation from the oral mucosa and jawbone. The main groups of prostheses that require pre-preparation surgeries are as follows:
\t- Complete (Total) Prostheses: In cases where there are no teeth left in the mouth, for the purpose of increasing the vacuum effect of palatal prostheses that transmit the entire chewing force to the jaw crest.
\t
- Partial (Segmental) Prostheses: To prevent prostheses that attach with clasps in cases of partial tooth loss from applying uneven pressure on the tissues in toothless areas.
\t
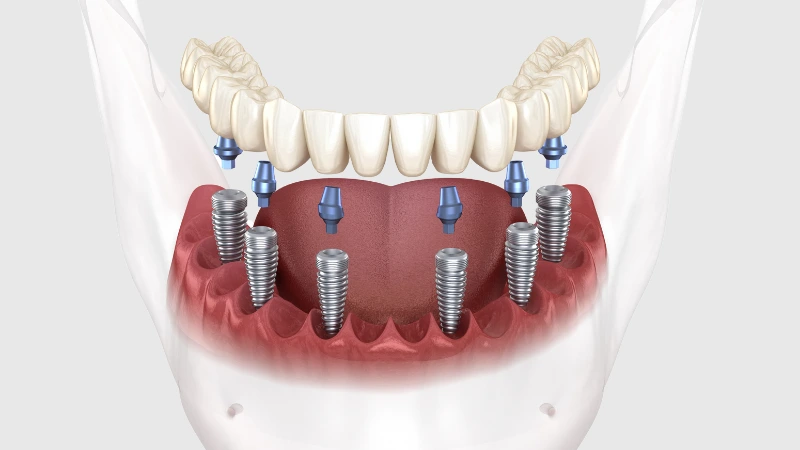
- Implant-Supported Removable Prostheses: In systems that are supported by artificial roots but also rest on the tissue, to ensure soft tissue integration.
What is the Relationship Between Pre-Prosthetic Surgery and Dental Prosthetic Applications?
The relationship between the two applications; should be an inseparable engineering whole that supports each other; the surgical procedure prepares a foundation (terrain) that is clean, healthy, and balanced for the prosthesis, while the prosthesis performs the chewing function uninterruptedly on this solid infrastructure.Just as the stronger and more even the foundation of a house is, the structure built on it will be more durable. In dentistry, removable prostheses work by getting support from the mucosa covering the jawbone. If there are bony indentations and protrusions, sharp peaks, or movable folded tissues beneath this mucosa, even a prosthesis made of the best material in the world will cause pain in that mouth and will shift during chewing.
The surgeon trims or repositions the tissues according to medical measurements to ensure the anatomical perfection of the dimensions the prosthodontist will take. When the tissues heal and take on a round and firm (fibrotic) curvature, the prosthesis tightly wraps this curvature like a vacuum. This biological compatibility ensures that the prosthesis functions for many years without damaging the tissue.
What Bone and Soft Tissue Modifications Can Be Made Within the Scope of Preprosthetic Surgery?
Modification spectrum; among bone procedures, there are torus (bone protuberance) removal and crest leveling (alveoloplasty); among soft tissue procedures, operations include the cutting of mobile hyperplastic (excess) tissues, removal of short frena (frenectomy), and increasing the depth of the vestibule (groove).The structure of the tissue to be intervened defines the class of the surgery. The fundamental approaches applied to two different tissue types are as follows:
Bone Tissue Operations Soft Tissue Operations Torus Resection: The trimming of bone protrusions found in the middle of the palate or under the tongue. Excision of Hyperplasia: Removal of irritated tissue and excess gum tissue from an old prosthesis using laser or scalpel. Alveoloplasty: Smoothing and leveling off sharp bone edges remaining after tooth extraction. Frenectomy: Cutting and releasing thick tissue bands that attach the lip, cheek, or tongue to the jaw. Crest Reduction: Aligning the crest tip by shortening it when there is no vertical space left for the prosthesis size. Vestibuloplasty: Surgically increasing the depth of the lip-cheek sulcus to ensure better retention of the prosthesis edges.
What Diagnosis and Imaging Methods Are Used Before Preprosthetic Surgery?
In the stage of diagnosis and visualization; in addition to the tactile examination performed by the physician, panoramic X-rays showing asymmetries and protrusions in the jawbone and dental volumetric tomographs reflecting the three-dimensional volume of the bone/height and the distance to the lower jaw nerve are utilized.It is generally not possible to determine the tissue thickness and the actual structure of the underlying bone with the naked eye. During a clinical examination, the doctor identifies the sharp points of the bone, painful protrusions, and the volume of movable soft tissue by palpating the gums with their fingers. However, the main factor that clarifies the surgical plan is the radiological data.
Especially if bone reshaping in the lower jaw is planned, the proximity of the nerve canal (mandibular canal) that provides sensation to the lower lip should be measured with tomographs. When performing bone reduction (alveoloplasty), ensuring that no pressure is exerted on the nerve is guaranteed through the millimetric depth analyses provided by these diagnostic tools. In soft tissue surgeries, the need for radiography is lower, and digital measurements obtained with intraoral optical scanners guide the planning.
How Does the Healing Process Progress After Preprosthetic Surgery?
Healing process; the rapid bonding of epithelial cells at the site of soft tissue cuts within the first one to two weeks (suture removal phase) and the transformation of underlying bone or mucosal repair into a firm, pressure-resistant (fibrotic) tissue over months occurs in a cellular cycle.Since the vascularization of the mucosal tissue is quite high, the healing of superficial wounds after soft tissue operations progresses rapidly. Patients can return to their routine eating habits within a few days. Especially in laser frenulum (band) cuts or tissue removals, bleeding remains at a minimal level and the tissue recovers in a short time.
In operations involving bone arrangements, the main healing continues beneath the tissue. The bone typically requires a biological time of 4 to 8 weeks to regain its pure form and for the overlying gum tissue to reach a keratinized structure capable of withstanding the chewing forces of the prosthesis. The physician waits for this maturation phase, where the tissue completely incorporates into its final volume for measurements; otherwise, measurements taken too early can lead to the loosening of the prosthesis with the shrinkage of the gum months later.
How Long Can Preprosthetic Surgical Procedures Take?
Operation duration; it generally varies between 20 minutes to one hour for a single area depending on the width of the tissue area to be intervened, the anatomical difficulty of the procedure originating from bone or mucosa, and the state of regional anesthesia to be applied.Laser-assisted small soft tissue incisions (for example, lip frenulum removal) are practical clinical steps that can be completed in just a few minutes after the anesthesia effect sets in. However, the surgical exposure and aesthetic suturing of the large bone remnants found scattered in different areas of the jaw (tori) require a detailed procedure that takes time.
If multiple tooth extractions along with alveoloplasty (bone reshaping) are planned as part of the preparation procedure before the prosthesis, the session duration may extend somewhat. Due to the patient being under anesthesia, no pain is felt throughout the procedure, and the process is managed according to the planning determined by the physician in advance.
How to Care for the Mouth After Preprosthetic Surgery?
Post-operative oral care; involves avoiding mechanical brush contact with the area where the stitches are located, ensuring the hygiene of that area only by rinsing with chlorhexidine mouthwash recommended by the doctor, and cleaning the other parts of the mouth from bacterial plaque using the usual brushing routine.The surgical areas where stitches are placed are quite open to irritation in the first days. Using hard brush strokes or forceful mouth rinsing can cause tension on the stitches or separation of the wound edges. Therefore, until the doctor indicates otherwise, hygiene maintenance in the wound area is provided only with chemical liquids. When using mouthwash, gently swishing the liquid in the mouth and avoiding forceful rinsing is essential to protect the clot in the wound area.
After the wound tissue has merged and stitches are removed by the doctor, one can switch to using extra soft (surgical type) brushes and perform gentle scrubbing motions as if massaging the area. Once the maturation of the tissues is fully completed, a sterile and comfortable oral flora will be achieved for the new prosthetic phase.
Why is Follow-up Examination Important After Pre-prosthetic Surgery?
The clinical necessity of control examinations; monitoring the performance of wound lips’ joining, preventing food accumulation in the area by removing surgical stitches, and most importantly, confirming tissue compatibility (tightness) by the physician is crucial for transitioning to the stage of measuring the new prosthesis.During this control session conducted in the first one or two weeks following the surgical intervention, the physician checks whether the tissues are free from edema. Since the sutures can cause local irritations (redness) by leading to plaque accumulation when left in the oral environment for a long time, they are gently removed during this appointment.
Prosthesis construction does not begin immediately. The bone and gum must recover from the surgical trauma and reach their final volume. The physician monitors the tissue’s healing rate during control sessions; when the tissues become stable and hard (keratinized), they approve the entry of measuring jaw models into the mouth, thus starting the prosthesis construction phase.
Can Preprosthetic Surgery be Planned Together with Other Oral and Dental Treatments?
Yes, it is often integrated into medical planning. These procedures can be performed simultaneously, either by removing infected tooth roots that have remained in the mouth (tooth extraction) or by placing a titanium artificial root (implant) as part of a combined approach.Practices in dentistry create a strong infrastructure. Especially if the bone around the teeth to be extracted is already irregular, the dentist reshapes the sharp edges of the bone in that area with burrs while the patient is still under anesthesia immediately after extracting the tooth (alveoloplasty). Thus, the patient is spared the burden of a second surgical operation when they reach the prosthetic phase in the following months.
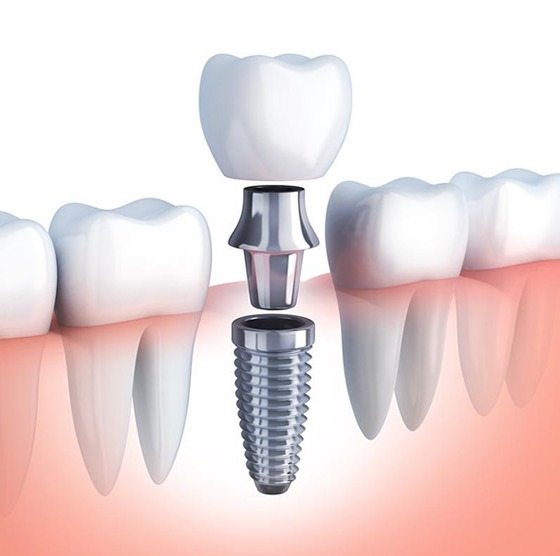
A similar integration is also observed in implant treatments. When the titanium body is placed in the jaw, if the bone is very sharp in the horizontal plane, the sharp area is reshaped according to preprosthetic surgical principles to ensure that the implant stays within the bone, thereby creating a uniform bone thickness, and artificial roots are placed on a wider platform.
How is Personalized Treatment Planning Done in Preprosthetic Surgery?
Custom Design for the Individual; involves surgically designing a support form that will conform to the anatomy of that individual and stabilize their prosthesis, based on the analysis of the chin curvature, mucosal tissue thickness, and lip-cheek mobility during speech, using digital or physical measurements.Every person’s oral anatomy and muscle dynamics are different. In one patient, the gum may be very thin and bone protrusions very pronounced; while in another patient, excessively mobile soft tissues may create fluctuations on the surface where the prosthesis will sit. The physician determines precisely which areas will bear pressure from the prosthesis type (fixed, movable, with hooks, etc.) that the patient will use.
The bone tolerance or soft tissue resistance in areas corresponding to these pressure points outlines the operative strategy. In the processes at Izmir Avrupadent, the limits of the procedure are defined according to the patient’s radiological findings and muscle strength. By avoiding unnecessary tissue loss (minimally invasive), it is ensured that the jaw functions as a mechanical cushion for the prosthesis after healing.
Successful prosthetic fabrication is possible with a thorough physical assessment. If the patient has an old prosthesis, the doctor examines the areas of tissue damage created by that prosthesis. Traumatic ulcers or mucosal layers caused by the prosthesis are identified. Areas with rough surfaces on the bone and sharp alveolar edges (of the jaw crest) that could cause pain under the prosthesis are mapped.
The extent to which the patient’s lip and cheek muscles (facial expressions) retract the connective tissue is tested while speaking. This retraction force helps to determine whether the short frenula (attachments) tied to the gum line will displace the prosthesis. In patients using blood-thinning agents, it is essential to establish a consultation with the physician before the operation to ensure the bleeding situation is secured, which forms the medical aspect of the process.
What Steps Are Taken in Preprosthetic Surgical Process?
The steps taken to support tissue repair and arrange anatomical boundaries are carried out successively while respecting surgical principles. The steps followed in a basic intervention are as follows:
-
\t
- • Anesthesia Application: The numbing of the nerve fibers surrounding the operative area with local agents to ensure clinical comfort.
- • Tissue Incision and Separation: The removal of excess tissues using a scalpel or laser or the gentle separation of the mucosa like a delicate flap to reach the underlying bone.
- • Bone Shaping (Alveoloplasty): The smoothing and rounding of irregular bone edges by filing with special surgical burs.
- ▪ Washing and Stitching (Suturing): Closing the area of work by stitching it in a way that will be compatible with the new prosthetic borders after washing the tissue with physiological serums.
\t
\t
What Should Be Considered Before Preprosthetic Surgery?
Keeping the microbial load of the working area at a minimum during surgical interventions prevents complications that may arise during the healing period. The patient should carefully clean their teeth and gums before the operation, and if recommended, should use antiseptic mouthwashes. Prescribed blood pressure medications or diabetes pills should continue to be taken at routine times.
Due to the procedure being performed under local anesthesia, it is recommended that the patient arrives for the appointment in a slightly fasting and rested state to keep the hospital’s blood sugar and blood pressure levels stable. If the use of tobacco that slows down cellular repair is present, limiting this habit before the day of the operation supports the repair process from a clinical perspective.
What Should Be Considered After Preprosthetic Surgery?
After surgical procedures, slight swelling in the cheek or lip area and tiny leaks observed inside the mouth are a natural response of cellular repair. Applying ice compresses in the first 24 hours significantly limits this swelling. It is advisable to swallow to move the area in the first days, as chewing, drinking with a straw, or forcefully gargling may disrupt the clot formed in the wound area.
After the operation, if the physician has not adapted the inside of the old prosthesis with a soft lining material, it may be advised that the patient avoid wearing the old prosthesis for a few days to prevent pressure on the sutured area. Acidic, hot, and spicy foods should be removed from the menu as they may irritate the healing mucosa. The use of tobacco should be restricted until the wound has closed, as it can impair tissue blood flow.
Which Prosthetic Treatments Are Evaluated Before Preprosthetic Surgery?
The correction of tissue surface is often planned in wide surface restorations that derive their foundation from the oral mucosa and jawbone. The main groups of prostheses that require pre-preparation surgeries are as follows:
-
\t
- Complete (Total) Prostheses: In cases where there are no teeth left in the mouth, for the purpose of increasing the vacuum effect of palatal prostheses that transmit the entire chewing force to the jaw crest.
- Partial (Segmental) Prostheses: To prevent prostheses that attach with clasps in cases of partial tooth loss from applying uneven pressure on the tissues in toothless areas.
- Implant-Supported Removable Prostheses: In systems that are supported by artificial roots but also rest on the tissue, to ensure soft tissue integration.
\t
\t
What is the Relationship Between Pre-Prosthetic Surgery and Dental Prosthetic Applications?
Just as the stronger and more even the foundation of a house is, the structure built on it will be more durable. In dentistry, removable prostheses work by getting support from the mucosa covering the jawbone. If there are bony indentations and protrusions, sharp peaks, or movable folded tissues beneath this mucosa, even a prosthesis made of the best material in the world will cause pain in that mouth and will shift during chewing.
The surgeon trims or repositions the tissues according to medical measurements to ensure the anatomical perfection of the dimensions the prosthodontist will take. When the tissues heal and take on a round and firm (fibrotic) curvature, the prosthesis tightly wraps this curvature like a vacuum. This biological compatibility ensures that the prosthesis functions for many years without damaging the tissue.
What Bone and Soft Tissue Modifications Can Be Made Within the Scope of Preprosthetic Surgery?
The structure of the tissue to be intervened defines the class of the surgery. The fundamental approaches applied to two different tissue types are as follows:
| Bone Tissue Operations | Soft Tissue Operations |
|---|---|
| Torus Resection: The trimming of bone protrusions found in the middle of the palate or under the tongue. | Excision of Hyperplasia: Removal of irritated tissue and excess gum tissue from an old prosthesis using laser or scalpel. |
| Alveoloplasty: Smoothing and leveling off sharp bone edges remaining after tooth extraction. | Frenectomy: Cutting and releasing thick tissue bands that attach the lip, cheek, or tongue to the jaw. |
| Crest Reduction: Aligning the crest tip by shortening it when there is no vertical space left for the prosthesis size. | Vestibuloplasty: Surgically increasing the depth of the lip-cheek sulcus to ensure better retention of the prosthesis edges. |
What Diagnosis and Imaging Methods Are Used Before Preprosthetic Surgery?
It is generally not possible to determine the tissue thickness and the actual structure of the underlying bone with the naked eye. During a clinical examination, the doctor identifies the sharp points of the bone, painful protrusions, and the volume of movable soft tissue by palpating the gums with their fingers. However, the main factor that clarifies the surgical plan is the radiological data.
Especially if bone reshaping in the lower jaw is planned, the proximity of the nerve canal (mandibular canal) that provides sensation to the lower lip should be measured with tomographs. When performing bone reduction (alveoloplasty), ensuring that no pressure is exerted on the nerve is guaranteed through the millimetric depth analyses provided by these diagnostic tools. In soft tissue surgeries, the need for radiography is lower, and digital measurements obtained with intraoral optical scanners guide the planning.
How Does the Healing Process Progress After Preprosthetic Surgery?
Since the vascularization of the mucosal tissue is quite high, the healing of superficial wounds after soft tissue operations progresses rapidly. Patients can return to their routine eating habits within a few days. Especially in laser frenulum (band) cuts or tissue removals, bleeding remains at a minimal level and the tissue recovers in a short time.
In operations involving bone arrangements, the main healing continues beneath the tissue. The bone typically requires a biological time of 4 to 8 weeks to regain its pure form and for the overlying gum tissue to reach a keratinized structure capable of withstanding the chewing forces of the prosthesis. The physician waits for this maturation phase, where the tissue completely incorporates into its final volume for measurements; otherwise, measurements taken too early can lead to the loosening of the prosthesis with the shrinkage of the gum months later.
How Long Can Preprosthetic Surgical Procedures Take?
Laser-assisted small soft tissue incisions (for example, lip frenulum removal) are practical clinical steps that can be completed in just a few minutes after the anesthesia effect sets in. However, the surgical exposure and aesthetic suturing of the large bone remnants found scattered in different areas of the jaw (tori) require a detailed procedure that takes time.
If multiple tooth extractions along with alveoloplasty (bone reshaping) are planned as part of the preparation procedure before the prosthesis, the session duration may extend somewhat. Due to the patient being under anesthesia, no pain is felt throughout the procedure, and the process is managed according to the planning determined by the physician in advance.
How to Care for the Mouth After Preprosthetic Surgery?
The surgical areas where stitches are placed are quite open to irritation in the first days. Using hard brush strokes or forceful mouth rinsing can cause tension on the stitches or separation of the wound edges. Therefore, until the doctor indicates otherwise, hygiene maintenance in the wound area is provided only with chemical liquids. When using mouthwash, gently swishing the liquid in the mouth and avoiding forceful rinsing is essential to protect the clot in the wound area.
After the wound tissue has merged and stitches are removed by the doctor, one can switch to using extra soft (surgical type) brushes and perform gentle scrubbing motions as if massaging the area. Once the maturation of the tissues is fully completed, a sterile and comfortable oral flora will be achieved for the new prosthetic phase.
Why is Follow-up Examination Important After Pre-prosthetic Surgery?
During this control session conducted in the first one or two weeks following the surgical intervention, the physician checks whether the tissues are free from edema. Since the sutures can cause local irritations (redness) by leading to plaque accumulation when left in the oral environment for a long time, they are gently removed during this appointment.
Prosthesis construction does not begin immediately. The bone and gum must recover from the surgical trauma and reach their final volume. The physician monitors the tissue’s healing rate during control sessions; when the tissues become stable and hard (keratinized), they approve the entry of measuring jaw models into the mouth, thus starting the prosthesis construction phase.
Can Preprosthetic Surgery be Planned Together with Other Oral and Dental Treatments?
Practices in dentistry create a strong infrastructure. Especially if the bone around the teeth to be extracted is already irregular, the dentist reshapes the sharp edges of the bone in that area with burrs while the patient is still under anesthesia immediately after extracting the tooth (alveoloplasty). Thus, the patient is spared the burden of a second surgical operation when they reach the prosthetic phase in the following months.
A similar integration is also observed in implant treatments. When the titanium body is placed in the jaw, if the bone is very sharp in the horizontal plane, the sharp area is reshaped according to preprosthetic surgical principles to ensure that the implant stays within the bone, thereby creating a uniform bone thickness, and artificial roots are placed on a wider platform.
How is Personalized Treatment Planning Done in Preprosthetic Surgery?
Every person’s oral anatomy and muscle dynamics are different. In one patient, the gum may be very thin and bone protrusions very pronounced; while in another patient, excessively mobile soft tissues may create fluctuations on the surface where the prosthesis will sit. The physician determines precisely which areas will bear pressure from the prosthesis type (fixed, movable, with hooks, etc.) that the patient will use.
The bone tolerance or soft tissue resistance in areas corresponding to these pressure points outlines the operative strategy. In the processes at Izmir Avrupadent, the limits of the procedure are defined according to the patient’s radiological findings and muscle strength. By avoiding unnecessary tissue loss (minimally invasive), it is ensured that the jaw functions as a mechanical cushion for the prosthesis after healing.
Preprosthetic Surgery hakkında sıkça sorulan sorular ve cevapları
Bu işlem sonrası protez uygulaması nasıl planlanır?
Preprotez cerrahisi sonrası protez uygulaması, fonksiyon ve estetiği en iyi şekilde sağlamak için dikkatlice planlanır. Bu süreç, sert ve yumuşak dokuların ayrıntılı değerlendirilmesini içerir; görsel muayene, palpasyon ve radyografik incelemelerle uygun protez tasarımı belirlenir. Ayrıca kemik kalitesi, sinüs anatomisi ve nörovasküler yapılar gibi faktörleri değerlendirmek için bilgisayarlı tomografi (BT) gibi gelişmiş görüntüleme yöntemleri kullanılır. Preoperatif modeller ve cefalometrik analizler, dişler arasındaki ilişkiler ve protezlerin takılma yolları hakkında bilgi sağlar. Bilgisayar destekli tasarım (CAD) teknolojisi ve cerrahi kılavuzlar, implant yerleştirme doğruluğunu artırarak son protezin anatomik yapıya uyumlu olmasını sağlar. Tüm bu planlama, hastanın ihtiyaçlarına ve beklentilerine uygun, stabil, konforlu ve fonksiyonel bir protez sonucu elde edilmesini hedefler.
Diş hekimliğinin hangi uzmanlık birimi Preprotetik Cerrahi operasyonlarını gerçekleştirmektedir?
Kemik ve yumuşak dokuların kesilip şekillendirilmesini gerektiren bu hassas doku işlemleri Ağız, Diş ve Çene Cerrahisi uzmanlık alanınca planlanıp yürütülür.
Tesadüfen rutin muayenede saptanan ağrısız doku büyümeleri için Preprotetik Cerrahi teşhisi konulabilir mi?
Dudak ve yanak ısırmasına bağlı oluşan ağrısız fibromlar (doku yumruları) protezin dengesini bozacağı için tespit edildikleri an alınmaları yönünde teşhis konur.
Sadece müdahale edilecek bölgenin lokal olarak uyuşturulması Preprotetik Cerrahi işlemi için yeterli midir?
Çenenin tümüne değil, sadece operasyon yapılacak olan küçük doku alanına uygulanan anestezi hastanın hiçbir acı hissetmemesi için fazlasıyla yeterlidir.
Dışarıdan buz (soğuk kompres) uygulaması Preprotetik Cerrahi ödemini ilk yirmi dört saatte nasıl yatıştırır?
Uygulanan buz damarları anında büzerek dokulara fazla sıvı hücum etmesini fiziksel olarak engeller, böylece şişlik erken aşamada tamamen bastırılır.
Operasyon günü ılık püre veya çorba gibi gıdaların tüketimi Preprotetik Cerrahi dokularını yormamak adına uygun mudur?
Tanesiz ılık çorbalar veya ezilmiş püreler sert bir çiğneme basıncı gerektirmediği için dikişleri hiç zorlamayan en ideal ve doyurucu beslenme şeklidir.
Şehir dışından Avrupadent İzmir’e gelecek hastalar Preprotetik Cerrahi planlaması için mevcut tomografilerini uzaktan iletebilir mi?
Uzaktan iletişim numaralarımız üzerinden dijital röntgenlerinizi göndererek, kliniğimize doğru yola çıkmadan önce cerrahlarımızdan ön bir teşhis almanız oldukça kolaydır.
Cerrahi işlemler sonrası komplikasyon riski nedir?
Preprotetik cerrahi, protez rehabilitasyonu için ağız boşluğunun hazırlanmasını amaçlayan bir işlemdir ve enfeksiyon, kanama, iyileşme gecikmesi gibi komplikasyon riskleri taşır. Postoperatif enfeksiyon oranları, yüzeyel cerrahi alan enfeksiyonları için %1,9 ile %1,3 arasında, derin enfeksiyonlar için ise %0,6 ile %0,4 arasında değişmektedir. Preprotetik cerrahilerle ilgili spesifik veriler sınırlı olsa da bu oranlar genel komplikasyon risklerini yansıtmaktadır. Riskler ve faydalar hakkında daha fazla bilgi almak için bir uzmanla görüşmek önemlidir.
Protezin vuruk yapmasını önlemede Preprotetik Cerrahi kalıcı bir çözüm sunar mı?
Alt zemindeki sivri kemik veya yığılmış et fiziksel olarak ortadan kaldırıldığı için, protez dokuya tam olarak adapte olur ve kronik vuruk sorunları kalıcı olarak çözülür.
Planlanan Preprotetik Cerrahi öncesinde ağız hijyenini sağlamak için diş taşı temizliği şart mıdır?
Operasyon alanının çevresindeki bakterilerin uzaklaştırılması, kesi yapılacak yaranın sonrasında iltihap kapmaması için çok değerli bir hazırlık adımıdır.
Hastanın bilinci açıkken Preprotetik Cerrahi sürecinin tamamlanması diş hekimliğinde standart mıdır?
Tüm işlemler sırasında hasta uyanıktır, hekimin yönlendirmeleriyle uyum içinde kalır ve sıfır sızıyla süreci gayet sakin bir şekilde izleyebilir.
Şiddetli tükürme veya ağız çalkalama hareketleri Preprotetik Cerrahi yarasındaki pıhtıyı bozar mı?
Bu eylemler ağız içinde vakum (basınç) etkisi yaratarak yara yerindeki yeni mikro pıhtıları sökebileceğinden ilk gün kesinlikle tükürülmemelidir.
Pipet kullanarak sıvı tüketmek Preprotetik Cerrahi yarası üzerinde vakum yaratarak kanamayı başlatır mı?
İçecek çekerken oluşan güçlü emme basıncı yara içindeki taze tıkaçları yerinden sökebileceği için ilk günlerde tüm sıvılar sadece bardaktan direkt içilmelidir.
Avrupadent İzmir laboratuvarları, Preprotetik Cerrahi sonrası yapılacak kalıcı protezlerin tasarımını yeni kemik formuna göre hızla üretir mi?
İyileşen ve pürüzsüzleşen çenenizden alınan yeni ölçüler, entegre dijital laboratuvarlarımızda hızla işlenerek protezinizin size konforla ulaşması sağlanır.
Preprotetik cerrahi hangi durumlarda zorunludur?
Preprotez cerrahisi, diş protezlerinin düzgün bir şekilde uyum sağlamasını ve fonksiyon göstermesini engelleyen anatomik durumlar olduğunda gereklidir. Bu durumlar arasında belirgin alveolar yastık çekilmesi, protez stabilitesini ve tutuculuğunu bozan, kemik çıkıntıları veya alt kesikler, protez yerleşimini engelleyen, yumuşak doku anormallikleri (Örneğin aşırı hareketli veya hipertrofik doku) ve çene ilişkilerindeki olumsuzluklar yer alır. Preprotez cerrahisinin temel amacı, fonksiyonel ve uyumlu bir ağız yapısı oluşturarak, protezlerin çiğneme, konuşma ve estetik açıdan etkili bir şekilde geri kazandırılmasını sağlamaktır.
Protez takıldığında acı veren kemik dikensi çıkıntıları Preprotetik Cerrahi muayenesinde nasıl tespit edilir?
Hekim el yordamıyla çene hattını kontrol eder ve ince filmlerle batan noktaları saptayarak bu cerrahinin sınırlarını belirler.
Ağız içinde akut bir iltihap varken Preprotetik Cerrahi uygulanır mı yoksa yatışması mı beklenir?
İltihaplı ortam uyuşturucu solüsyonun etkisini ve yara iyileşmesini bozacağından, klinik olarak şişliğin tamamen yatışması beklenerek işlem planlanır.
Kemiğe ulaşmak için Preprotetik Cerrahi sırasında diş etinin ufak bir pencere gibi aralanması (flep) gerekir mi?
Sivri kemiklerin üzerindeki diş eti dokusu özel uçlarla kibarca sıyrılarak açılır, böylece alttaki kemik doğrudan görülerek hatasız işlem yapılır.
İlk günlerde sızıntı şeklindeki açık pembemsi tükürük Preprotetik Cerrahi sonrası doğal bir iyileşme belirtisi midir?
Tükürük sızıntıyı geniş gösterdiği için kanama varmış gibi algılanır; bu açık renkli hafif pembemsi doku sızıntıları iyileşmenin ilk günlerinde son derece olağandır.
Susam veya çekirdek gibi küçük taneli gıdalar Preprotetik Cerrahi dikişlerinin arasına kaçarak tahriş yapar mı?
Kesim hattına yapışan bu sert parçacıkların fırça vurulmayan o bölgeden temizlenmesi zor olacağından ve batma yapacağından dolayı menüden çıkarılmalıdır.
Contact Us for Preprosthetic Surgery in Izmir
Preprosthetic surgery is a surgical treatment method that involves preparing the jawbone and soft tissue structure for prosthetic application prior to the placement of prosthetics. At AvrupaDent, this treatment is performed by dentists within the framework of a treatment plan suitable for the patient’s oral and dental health. You can contact us for detailed information about the treatment process.İletişime Geçin
- Güncelleme tarihi:25 Sep 2026