

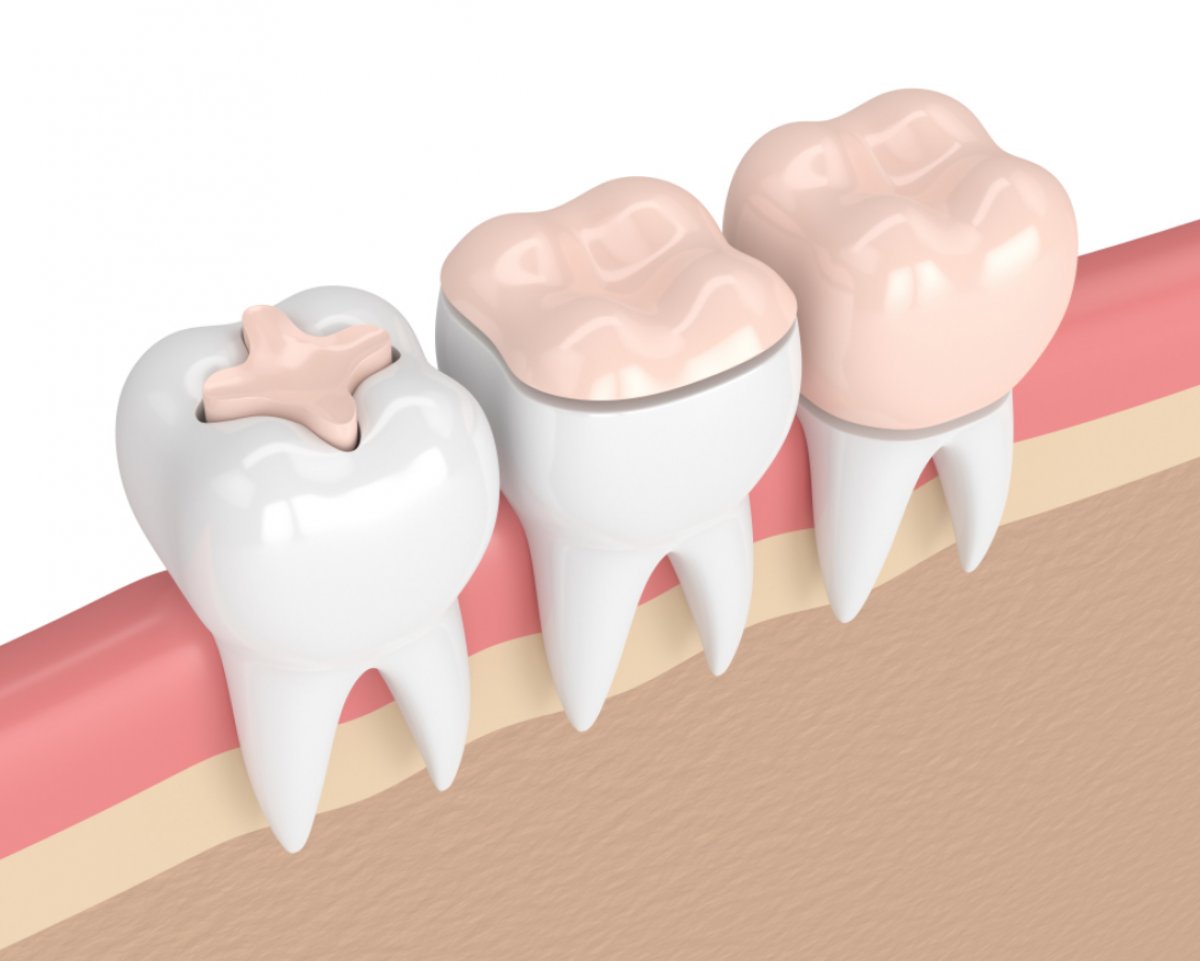
What Are Porcelain Inlays / Onlays?
Tissue-preserving (conservative) approaches are prioritized in clinical dentistry. After a tooth is prepared, the remaining healthy enamel and dentin must be supported by different materials if they do not have the strength to withstand the forces exerted by a standard filling material. Inlay and onlay restorations are laboratory-produced porcelain fillings that integrate into the tooth like pieces of a three-dimensional puzzle, complementing only the missing part of the tooth. Inlay restorations fill smaller cavities that do not include the cusps of the tooth, while onlay restorations cover one or more cusps of the tooth, thereby restoring the chewing surface more extensively.
At the Avrupadent clinics located in İzmir, porcelain inlay and onlay filling applications are planned based on the principle of preserving the individual’s own natural tooth structure. Instead of reducing the entire tooth, only the damaged area is removed, preserving the remaining healthy structure. These fillings, produced from ceramic or reinforced glass ceramic blocks, are custom-designed to fit perfectly in accordance with the anatomical grooves, external contours, and contact points with adjacent teeth.
In Which Situations Are Porcelain Inlays / Onlays Applied?
Our chewing system exerts a high amount of mechanical force on the teeth during the closure of the upper and lower jaws. When a large cavity is cleaned, the side walls of the tooth can become quite thin. When a classic composite filling is placed between these thin walls, over time, due to chewing pressure, there is a risk of vertical cracks or fractures forming in the remaining walls of the tooth. The main clinical situations where this method is planned can be summarized as follows:
| Area of Application | Clinical Explanation and Effect |
|---|---|
| Large Cavity Lesions | Providing structural integrity in tissue losses affecting more than half of the chewing surface. |
| Endodontically Treated Teeth | Protecting the fragile tooth tissue that has lost vitality after root canal treatment by supporting it with a ceramic material. |
| Renewal of Old Restorations | Replacing it when large surface amalgam (gray) or composite fillings lose their tightness. |
| Interdental Spaces (Diastema) | Creating a shape that prevents food entrapment in cases where the contact point with neighboring teeth is weak. |
How Are Porcelain Inlay / Onley Fillings Applied?
The procedure is similar to classic crown procedures; however, the amount of tooth reduction is much lower. Initially, local anesthesia is applied to the relevant area, ensuring the patient’s comfort during the procedure. The fractured tissues are removed using specialized high-speed rotary instruments. In the remaining healthy areas of the tooth, specific adjustments in millimeters are made to ensure the retention of the upcoming ceramic filling.
After preparing the cavity (empty space), an anatomical replica of the tooth is taken using digital intraoral scanners or silicone-based measuring materials. In the laboratory, the porcelain filling is shaped to establish a complete closure relationship with adjacent teeth and opposing teeth. During the manufacturing process, the cavity is temporarily filled to prevent tooth sensitivity. In the final appointment, the temporary material is removed, and the porcelain filling is tested on the tooth. Once the fit is confirmed, strong adhesive agents (adhesives) chemically bonded to enamel and dentin tissue are used to permanently fix the restoration.
Who Can Benefit from Porcelain Inlays / Onlays?
The suitability of a restorative treatment depends largely on the person’s age and the size and location of the defect (cavity) in the tooth. For patients who want to preserve existing structure instead of losing more tooth tissue (capping), inlay and onlay applications provide a significant alternative in cases of severe damage where traditional fillings frequently break or fail.
On the other hand, in patients with severe teeth grinding (bruxism) issues, the planning of restorations requires special attention. If a person has untreated severe bruxism, the excessive vertical loads placed on ceramic restorations can lead to material fatigue over time. In such cases, practitioners may include protective supportive measures in the procedure, such as using a night guard post-procedure.
Which Teeth Are Suitable for Porcelain Inlays / Onlays?
In human anatomy, the front incisors are responsible for the cutting action, while the back molars take on the grinding action. The chewing pressure during the grinding function is highest in the posterior areas. Since porcelain inlays and onlays possess the mechanical strength to withstand this high pressure, they are particularly preferred for compensating for significant tissue loss in molars.
When material loss occurs in anterior group teeth, porcelain laminates (leaf porcelains) or aesthetic composite restorations, which differ in structure, are typically brought to the forefront. However, in molars with a tubercle (cusp) structure, reproducing that contour anatomically in a laboratory setting enhances functional adaptation.
How is an Evaluation Made Before Porcelain Inlays / Onlays?
The durability of any restorative procedure depends on the health of the tooth it is applied to and the surrounding tissues. The dentist first determines whether they can reach the pulp (nerve) chamber of the cavity. If the inflammation has reached the nerve chamber, it is a medical necessity to perform root canal treatment on the tooth roots before restoration.
In addition to radiological examinations, the dynamics of the patient’s occlusion (chewing) are analyzed. By analyzing the contact points (contact points) of the opposing tooth, the areas where the overlay or inlay filling will be subjected to force are calculated. If the necessary clinical conditions are met, preparations for the production of porcelain filling are started.
What Should Be Considered Before Porcelain Inlay / Onlay Fillings?
The quality of the impression-taking process in restorative dentistry is of great importance. The fit of porcelain restorations at the tooth and gum boundary is expected to be millimetric. If the patient has significant tartar buildup or inflammation-related gum bleeding in their mouth, bleeding during the impression-taking can compromise the clarity of the impression material. Therefore, it may be necessary to perform a general dental cleaning before inlay/onlay appointments.
Patients should also inform their doctors about any chronic discomforts they may have and the medications they are taking regularly as part of the medical process. Arriving at the clinic with personal oral hygiene ensured and after brushing will make the process comfortable for both the doctor and the patient.
How Many Sessions Are Needed to Complete Porcelain Inlays/Onlays?
In two-session approaches, the damaged areas on the patient’s tooth are cleaned on the first day. The measurements of the prepared tooth form are taken and sent to the laboratory. During the production period between the measurements and the second session (usually 3-5 days), the patient’s tooth is covered with a temporary filling material to prevent sensitivity.
In today’s technology, if clinics have in-house milling units with fully integrated CAD/CAM systems, this process can be shortened to a single session. The measurement can be taken with digital scanners and produced in the device on the same day, which may be considered in some cases. In Avrupadent clinic plans, the number of sessions is clarified based on the patient’s case situation.
How Does the Application Process of Porcelain Inlay / Onlay Fillings Proceed?
Medical and technical details follow one another in a chain. The preparation of the dental cavity (carving) is done with specific openings that will support the structural thickness of the inlay or onlay filling. The dentist shapes the depth and width of the cavity based on the material’s resistance, as there is a risk of breaking in areas where the porcelain material is very thin. The stages of application are generally as follows:
-
\t
- • Clinical Preparation: The tooth is cleaned from decay, and protective base materials are placed in deep areas of the lower layer if necessary.
- • Measurement and Color Selection: A dental map is created with a digital scanner, and the porcelain color is determined to match the patient’s natural tooth tone.
- ▪ Production Phase: Dental technicians create restorations from ceramic blocks by sketching the anatomical form using software.
- ▪ Cementation (Permanent Construction): Porcelain prepared with special acid and bonding agents is fixed in a way that integrates as a single piece (monolithic) onto the tooth surface.
\t
What Should Be Considered After Porcelain Inlay/Onlay Restorations?
After the composite restoration is completed, the patient can perform the chewing function. However, since a new structure is added to the overall oral dynamics, it may take a few days for the muscles and opposing jaw teeth to biologically adapt to this new form. During this initial adaptation period, it is advised to avoid breaking hard and challenging foods in that area (for example, nuts, ice, hard candies).
Additionally, the porcelain surface itself does not chip or stain; however, inflammation of the gum tissue may develop at the boundary lines where the restoration joins the tooth, depending on plaque accumulation. For this reason, the edges of the porcelain filling must be kept free of bacteria through daily brushing and the use of dental floss.
Can Sensitivity Be Observed After Porcelain Inlay / Onlay Fillings?
The dental dentin layer contains thousands of microscopic channels (dentin tubules) that connect directly to the nerve chamber at the center. During the cleaning of decay, these channels are exposed. Although porcelain restoration may completely clog these channels with chemical agents, the bonding reaction of the agent may cause a mild, temporary reaction (post-operative sensitivity) in the pulp tissue.
This situation is considered a biological and natural response of the body to medical procedures. These leaks, which are expected to gradually diminish and disappear over days, can be comfortably managed with pain relievers suggested by the physician. If sharp pain lasting for weeks or severe pain under pressure occurs, it is clinically necessary to consult the clinic again.
What is the Difference Between Porcelain Inlays/Onlays and Traditional Fillings?
Both materials are designed to completely restore tissue loss in the teeth, but they differ in their structural strengths and anatomical compatibilities. While classic resin-based (composite) fillings provide satisfactory results in small cavities, when the cavity enlarges, a phenomenon called polymerization shrinkage may occur. These structural comparisons are as follows:
| Comparison Point | Porcelain Inlay / Onlay | Classic Composite Filling |
|---|---|---|
| Production Area | Indirect (Laboratory) manufacturing of dental products. | Direct (Clinical) manufacturing inside the mouth. |
| Mechanical Strength | High resistance to chewing forces thanks to the ceramic block structure. | Sufficient in small forces, brittle in wide gaps. |
| Wear and Color Change | Thanks to the glassy surface, it does not wear or change color. | Over time, the surface may wear, it can get colored with food (tea/coffee). |
| Device Compatibility | Designed to millimetric precision on the model, it effectively prevents food trapping. | Creating a contact point in a wide gap can be challenging for the dentist. |
What Materials Are Porcelain Inlays/Onlays Made From?
The selection of material is determined by the dentist according to the outer position where the filling will be placed (the front or back area of the tooth) and the chewing pressure applied by the patient. If the tooth is located in an area with high aesthetic visibility, e-max (lithium disilicate) or feldspathic porcelain materials that reflect light like a natural tooth can also be considered.
In the area of the second large molar, where most of the chewing force is applied, hybrid materials (ceramic and composite blends) with excellent shock-absorbing properties are preferred to prevent wear on opposing teeth. These high-tech materials support biological and aesthetic compatibility because they do not contain the substructure metals (which cause gray reflections) found in traditional porcelain restorations.
How Are Porcelain Inlays / Onlays Evaluated in Treatment Planning?
In Izmir Avrupadent, while planning procedures, a biomechanical analysis of the defect (tissue loss) is conducted. The more natural enamel tissue that is preserved in a tooth, the longer the duration of that tooth’s presence in the mouth structurally. In full crown (veneer) applications, it is necessary to remove an average of 1.5 – 2 mm of material from around the tooth.
In inlay and onlay restorations, only the previously excavated cavity area is refined; healthy side walls are not cut. The physician evaluates whether the tissue damage provides sufficient retention area (retention space) for these partial crowns by combining radiological examination and intraoral examination data. If there is adequate retention area, this method is included in the planning.
Why is the control examination after porcelain inlay/onlay fillings important?
The structure of the mouth is a dynamic system that is subject to constant pressure and movement. When a restoration is placed, the response of the lower jaw to different chewing angles (right, left, forward shift) is examined during the construction session with carbon papers; however, the actual clinical performance emerges after the use.
If a concentrated force is applied to a specific point of the restoration, it can be detected by the dentist during periodic visits every 6 months, and millimetric adjustments (polishing) can be made. This helps prevent potential fractures in the porcelain and excessive pressures that may damage the underlying tooth, thus preserving the long-term functional continuity of the tooth.
How Should the Care of Porcelain Inlays/Onlays Be Done?
Since the applied ceramic structure is not an organic tissue, it does not self-destruct and is not affected like natural enamel by acids. However, it should be noted that inlays and onlays are constructed on the main tooth. The natural enamel and dentin tissue of the patient located beneath or at the side borders of the ceramic remains exposed to bacteria in the oral environment.
In cases of inadequate hygiene, microbial dental plaque accumulation can occur at the boundary where the filling meets the tooth (marginal gap), potentially leading to the onset of new cavities (secondary cavities). To maintain the protective quality of the restoration, careful yet effective cleaning of these junction lines during brushing is essential.
How Long Does It Take to Prepare Porcelain Inlays / Onlays?
After the model cast or digital scanning process reaches the technician laboratory agreed upon by the clinic, the porcelain, pressed in special furnaces or milled from blocks, undergoes stages such as hardening and glazing. These chemical and physical stages require a specific technical duration.
In applications where clinical facilities have advanced technology and include 3D (three-dimensional) printer/milling machines (Chairside CAD/CAM), this period can be reduced to just a few hours within the same day. Your dentist will share the schedule with you based on the needs of your case.
Can Porcelain Inlays / Onlays Use Digital Measuring Technologies?
Digital technologies are advanced clinical tools that eliminate human errors (distortion, expansion, air bubbles) in modern restorative dentistry. The three-dimensional model obtained with an intraoral scanner is directly transferred to the laboratory’s design software via the internet within seconds. This method provides significant clinical comfort, especially for patients who experience nausea (gag reflex) in response to measuring materials.
The design specialist molds the inlay or onlay filling that will perfectly fit the tooth in a three-dimensional format on a computer screen and tests the contact movements with the lower jaw in the virtual environment. The approved design is sent to milling machines to be carved from blocks without manual intervention, achieving millimetric edge fit.
Porcelain Inlay / Onlay Fillings: Which Treatments Can Be Planned Together?
The mouth is an ecosystem, and treatments are interrelated and supportive. For example, if the cavity in the tooth is very deep, the first step is to clean the root canals (root canal treatment); the upper restoration of the tooth is completed with an onlay porcelain filling to protect against tooth fracture.
If the cavity borders extend significantly below the gum line, a minor surgical intervention (crown lengthening procedure) may be performed by gum specialists to ensure the health of the porcelain restoration and its retention on the tooth. After the gum is leveled and healed, the dimensions for the inlay/onlay are taken to achieve compatibility with the tissue biology.




