

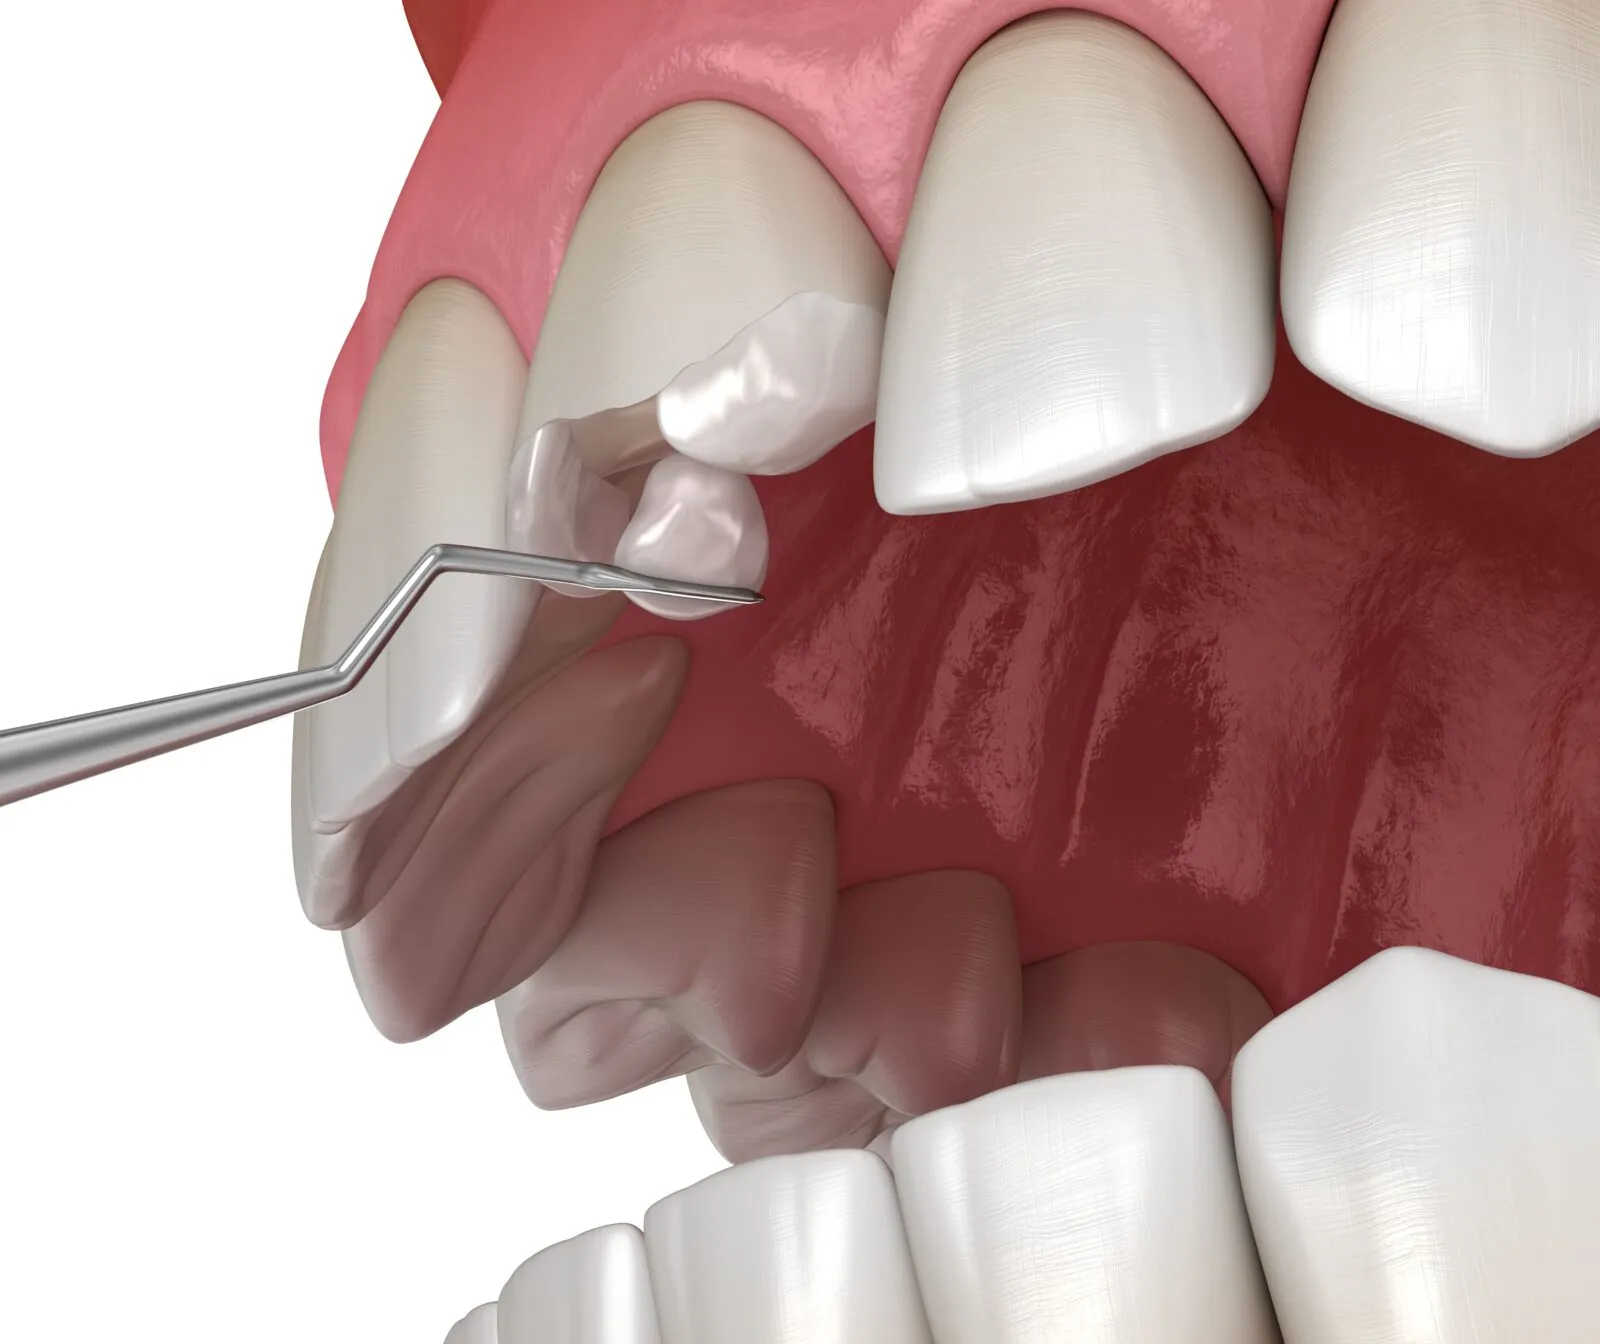
In which dental problems can porcelain veneers be applied?
The shape, color, and alignment asymmetries in the mouth and dental structure can be corrected to a minimal intervention level on the tooth, thanks to the material richness offered by modern medical disciplines. The applications of porcelain veneer (leaf porcelain), which is one of the fundamental pillars of the “minimal invasive” (tissue-preserving) approach in the field of Cosmetic Dentistry, are glass ceramic structures integrated into the tooth by etching a very thin layer of enamel, ranging from an average of 0.3 to 0.7 millimeters, only from the front surface visible to the lips. These thin ceramic leaves replicate the optical properties and light translucency of natural enamel tissue in a biomimetic way, allowing for the restoration of existing anatomical defects.
Unlike crown (covering) systems where the entire tooth is cut and reduced, porcelain veneers preserve the original tissue on the tongue and palate sides of the tooth. This structural feature serves as a decisive medical criterion regarding which clinical situations veneers can be applied to and which they cannot. The chemical bonding of the restoration to the tooth (adhesion) achieves a high chewing resistance by completely integrating the fragile glass structure of the material with the enamel. In Avrupadent clinical procedures, it is thoroughly analyzed to determine whether the patient’s current dental problems can be solved with these thin ceramic structures; closure dynamics, gum health, and the rate of material loss are evaluated in detail.
What role do porcelain veneers play in closing diastemas (gaps between teeth)?
Gaps between teeth known as diastemas are often caused by disproportionality between the sizes of the jawbone and the widths of the teeth. In particular, gaps between the two upper front incisors (centrals) can lead to phonetic (sound production) differences by altering airflow during speech and create visual asymmetry. In traditional approaches, patients are expected to undergo months-long orthodontic appliance (wire or plate) processes to close these gaps, whereas porcelain veneers offer anatomical restoration within a short clinical timeline.
In this clinical scenario, when applying porcelain veneers, the reduction made on the front surfaces of the teeth is kept much more limited; in fact, in some cases, it is even possible to take direct impressions of the tooth without touching it (prepless). Glass ceramics produced in a laboratory setting are designed to extend the existing tooth width in a millimetrically accurate manner towards the gap. Care is taken during this widening process to maintain both teeth’s symmetrical appearance and to avoid crushing the gingival papilla (the triangular tissue between teeth). Diastema cases are one of the primary indications (applicability) for porcelain veneers, yielding the most suitable and aesthetic results.
In Which Cases Are Porcelain Veneers Preferred for Stained and Discolored Teeth?
Changes in dental tissue color are examined in two separate categories: external and internal. External stains caused by the use of tea, coffee, or tobacco can usually be removed through surface cleaning and standard chemical whitening procedures. However, tetracycline stains, which integrate into the crystalline structure during the dental development phase through blood circulation, present themselves as gray or brown horizontal bands, and standard whitening agents may be insufficient to break these deep molecular bonds. Similarly, there is an internal color problem in teeth that have darkened or blackened due to loss of vitality and internal fluid loss after undergoing root canal treatment.
In cases of resistant color asymmetries, Aesthetic Dentistry procedures come into play with leaf porcelains. A thin layer is removed from the front surface of the tooth, and opaque ceramic powders with concealing properties are added to the inside surface of the prepared porcelain. This opaque layer blocks the reflection of the dark and flawed color underneath. To the outer surface of the porcelain, high transparency (translucent) glass ceramics are layered to create an illusion of a natural, vibrant, and light-permeable organic enamel tissue instead of a dull and matte appearance.
How Do Laminate Porcelains Function in the Repair of Broken or Cracked Tooth Structures?
Front teeth are the most anatomically exposed structures to trauma due to their positions. A fracture not only disrupts visual integrity but also exposes the dentin tubules beneath the enamel, leaving the tooth vulnerable to temperature sensitivity and bacteria from the external environment. In small chips, composite fillings are often used for repairs; however, if the fracture line is extensive or multiple micro-cracks exist in the tooth, the long-term durability or color stability of composite materials may be insufficient.
Porcelain laminates encase the tooth’s front surface like an armor in cases of significant tissue loss. The damaged area is completed with a solid body of glass-ceramic prepared in the laboratory. These veneers, produced using highly durable materials like lithium disilicate, chemically bond when constructed with special adhesive cements. This bond allows the porcelain to flex and integrate with the tooth, achieving biomechanical unity while exhibiting a strength close to the original fracture resistance of the tooth.
| Type of Tissue Loss | Restorative Contribution of Laminate Application |
|---|---|
| Large Incisal Edge Cracks | Completes the missing piece with glass-ceramic having high bulk fracture resistance. |
| Multiple Enamel Cracks (Crack) | Forms a protective and non-porous ceramic shield that prevents color infiltration into the cracks. |
| abrasion (Mechanical Wear) | It isolates tissue melting occurring in the outside neck (collar) region related to the surface. |
How is the Porcelain Veneer Alternative Evaluated in Alignment of Mild Crooked or Excessively Tilted Teeth?
Misalignment of teeth (spacing issues) is a condition that must be corrected by mobilizing the tooth roots in the bone through orthodontic (braces or clear aligners) treatment under normal conditions. However, if individuals do not have a major problem with their skeletal occlusion (bite) and if the malalignment only involves mild degrees of rotation affecting a few front teeth, extensive orthodontic treatments may not be preferred by patients. At this point, porcelain veneers are included in the plan as a medical option that creates an “orthodontic illusion.”
In mild crooked cases, the dentist performs a millimetric reduction of the protruding (anteriorly protruding) surfaces outside the jaw arch of the tooth. Volume is added by increasing the thickness of the porcelain material to the sections that remain behind the tooth (intrusive). Thus, even if the roots of the teeth remain in the same place, the visible crown parts appear to be arranged in a straight line on an even arch. However, this application has a medical limitation; if the crook is severe, a very deep tissue cut must be made to create porcelain, which carries the risk of damaging the nerve layer of the tooth (pulp). Therefore, planning a short-term orthodontic preparatory phase before applying veneers in severe cases is an approach that protects biological health.
Why Are Veneers Important in the Restoration of Worn and Shortened Teeth?
In a natural development process, the tips of anterior teeth have a slightly wavy transparent tissue called “mamelon” with high light translucency. Years of chewing activities, mechanical abrasion of foods, and acidic beverages lead to the wear and disappearance of this transparent layer. Teeth shorten, their incisal edges become flat (blunt), and the underlying yellowish dentin color becomes more evident due to enamel thinning. The shortening of tooth length also affects the vertical dimension of the face, making the lips appear thinner.
In cases of physiological or pathological wear, porcelain laminates not only preserve the existing tissue but also restore the lost biological volume to the tooth. The dentist designs the teeth to extend in length by one to two millimeters by calculating the patient’s lower lip curve and the phonetic limits while speaking. The tips of the produced laminates are processed in the laboratory with special glass-ceramic powders to reconstruct the lost “youthful translucency.” Thus, worn teeth regain their old functional vertical dimension and acquire a fresh and vibrant appearance visually.
How Are Tissue and Enamel Defects (Hypoplasia) in the Tooth Surface Treated with Laminates?
Systemic diseases encountered during the developmental stages of teeth in the womb or infancy, high fever, or nutritional deficiencies can disrupt the calcification (hardening) process of the enamel layer. This situation leads to structural defects known as “enamel hypoplasia” on the tooth surfaces. When teeth are in the mouth, small pits, horizontal striations, or yellow/brown enamel-like brittle spots can be found on them. These areas not only create an aesthetic problem but also provide a highly favorable environment for bacterial plaque accumulation and decay due to their porous surface.
Standard filling materials may struggle to repair these common tissue defects that cover the front surface of the tooth homogeneously. Porcelain laminates medically address this issue based on the principle of cleaning the problematic enamel surface in a very thin layer and then placing a smooth, glazed glass-ceramic leaf on top of it. This new surface, which is as smooth as glass, limits the adhesion of decay-causing bacteria and safeguards the tooth’s form, texture, and biological integrity.
How is the Use of Porcelain Laminate Planned for the Revision of Old and Stained Fillings?
Composite resin fillings placed on the front teeth due to historical wear or small cracks can change color over time due to the influence of oral fluids, food dyes, and tobacco usage. Micro-leakages occurring at the junction of the filling and the tooth enamel create brown streaks in that area. If there are multiple old fillings on several teeth, they create a complex visual tableau that resembles patches on the teeth and curves in different directions.
Aesthetic Dentistry practice evaluates transitioning to laminates, a more durable prosthetic solution, instead of repeatedly replacing these mismatched fillings with composite. During the procedure, these old fillings that primarily cause leakage are removed to reach a clean surface free of decay. Afterwards, a ceramic veneer (laminate) is designed in a single shade, maintaining a uniform surface finish. This approach restores optical harmony by gathering the fragmented and patched appearance under a single surface.
How Are Asymmetrical Tooth Dimensions and Shape Disorders Corrected with Porcelain Veneers?
One of the most frequently encountered anomalies in dental forms is the emergence of upper lateral incisors in a slender, pointed, wedge shape or very small sizes (peg lateral) instead of a normal tooth form. This condition creates a gap and disruption of form between the central incisors and canine teeth. This anomaly, which occurs in the area where facial symmetry is most pronounced, significantly affects the character of the smile.
In structural anomalies of this type, the application of porcelain laminates is usually realized with very minimal surface preparation (sometimes without even that). The missing anatomical parts of the tooth are completed with porcelain material by a technician in computer-aided design software (CAD) or in the laboratory. By achieving appropriate width and thickness for the tooth, the contact points with neighboring teeth are redefined. Integrating the naturally proportional dimensions of the asymmetric tooth, the surface and the dental arch (gold ratio) is made possible thanks to the structural bonding capability of the laminates.
| Type of Deformation | Contribution of Porcelain Laminate |
|---|---|
| Peg Lateral (Wedge Tooth) | Adding volume and width to the pointed and small tooth to achieve a normal incisor form. |
| Microdontia (Small Teeth) | Relative sizing of all the remaining small teeth behind the dental arch using golden ratio references. |
| Sharp/Pointed Canine Teeth | Softening the excessively sharp tips to create a more oval and symmetrical transition with the adjacent teeth. |
What are the Medical Limitations and Contraindications of Porcelain Laminate Applications (Situations Where They Cannot Be Applied)?
Knowing when a medical procedure will be successful is as important as predicting when it will be unsuccessful; this is a fundamental principle of treatment. The retention strength of porcelain veneers depends on the chemical bond (adhesion) to the outermost layer of the tooth, which is the enamel. If the enamel layer is almost nonexistent due to previous decay or large fillings, and if the underlying dentin layer is exposed, the bonding strength of the veneer to that tooth weakens biomechanically, increasing the risk of failure. In such cases, crown (covering) systems that surround the tooth 360 degrees should be preferred.
However, abnormalities in bite relationships are also contraindications. If the patient’s lower front teeth are meeting edge-to-edge with the upper front teeth, or if the lower jaw is positioned more forward than the upper jaw, horizontal shearing forces will act directly on porcelain veneers during chewing and speaking. Very thin glass-ceramic veneers cannot withstand this intense pressure and are likely to break or dislodge. In patients with severe bruxism (nighttime teeth grinding), the usual excessive pressure applied by the jaw muscles puts these thin veneers at risk. In such cases, prior orthodontic treatment, the use of night guards, or more durable full crown restorations must be pursued as different medical approaches.
According to Europadent Standards, what biological criteria are used for planning porcelain veneers?
A quality and long-lasting medical service relies on detailed data analysis during the preparation phase. Before a decision on porcelain laminate is made in Avrupadent’s process management, the patient’s overall intraoral flora and gum health are stabilized. In the presence of bleeding or swollen gums, it will not be possible to accurately measure the limits of the porcelain, so periodontal tissue health is prioritized first.
The intraoral model of the patient obtained using digital measuring systems (intraoral scanners) is combined in a computer environment with the patient’s facial lines. In smile design software, the amount to extend the teeth, how much to round the corners, or how to close gaps is virtually shaped, considering the existing anatomical limits of the teeth. Before any tooth reduction is made, a physical mock-up of this virtual design is applied for the patient. This way, the patient can experience how these ceramic restorations will look on their own face live, and only after achieving biological-aesthetic consensus are permanent procedures approved.
What are the Frequently Asked Questions?
1. Can porcelain laminate be applied to every tooth?
No, it is not preferable to apply them to teeth with insufficient enamel tissue, severely decayed, heavily filled, or where the habit of clenching cannot be controlled, due to the risk of adhesion and breaking of thin laminates in these situations.
2. Can gaps between teeth (diastema) be completely covered with veneers?
Yes, if the gaps between the teeth are not excessively wide, porcelain veneers can be expanded appropriately towards the sides (by adhering to the natural golden ratio) to cover these gaps with an organic appearance.
3. Can antibiotic stains be hidden with veneers?
Dark stains caused by antibiotics like tetracycline or fluorosis, which have penetrated the enamel and dentin, can be successfully masked from outside using opaque (covering) layers applied to the inner surface of the porcelain.
4. Can crooked teeth be corrected with veneers?
Optical corrections can only be made in cases of mild rotation (tilting) or minimal axis deviations; however, in cases of severe crookedness, deep cutting of the tooth is necessary to create porcelain veneers, making orthodontic alignment planning a biological necessity.
5. Can my tooth length be extended with veneers if it is very short?
Taking into consideration the lip stretch capacity and the curve of your lower lip’s smile arc, the length of your teeth can be extended with porcelain veneers to a level that does not violate functional and phonetic (speech) limits.
6. Can a front tooth that has undergone root canal treatment and has darkened have a veneer placed on it?
If the loss of material in the tooth is not excessive and the issue is only pigmentation, it can be covered with a veneer; however, if the tooth has become very fragile due to root canal treatment, it is more appropriate to use zirconium crowns that will wrap and protect the tooth all around.
7. How much will my tooth be reduced during the porcelain veneer application?
The front surface of the tooth is polished with a very limited enamel thickness ranging from 0.3 millimeters to 0.7 millimeters (about the thickness of a lens), protecting the back and lateral tissues of the tooth.
8. Can a laminate be made for just one tooth?
For instance, if there is a fracture or shape anomaly on just one tooth, the surface polishing, color transition, and transparency of the adjacent natural teeth can be carefully replicated in the laboratory and a singular laminate can be successfully integrated only on that tooth.
9. Does grinding down teeth create sensitivity with laminates?
On the contrary, the application of porcelain material and medical resins to cover the exposed sensitive dentin layer allows for overcoming the heat-cold sensitivity that develops due to external factors.
10. Do old fillings need to be removed to make a laminate?
If there are old composite fillings on the front surface of the tooth that have created marginal leakage, become discolored, or lost structural integrity, these fillings are removed and cleaned to ensure that there is no remaining decay beneath and that the porcelain adheres to healthy tissue.
11. If my jaw closes edge to edge, can I still get laminates?
In edge-to-edge closures, the lower teeth apply a severe and direct horizontal impact force on the cutting edges of the upper teeth, which significantly increases the risk of breaking thin laminates; this condition is an important contraindication for laminates.
12. Do laminates break in patients with teeth grinding (bruxism)?
Uncontrolled severe cases of bruxism can exert abnormal forces that may fracture ceramic structures; if laminates are to be applied to these patients, it is medically necessary to create night splints to be used during sleep at the end of the treatment.
13. How are enamel defects (hypoplasia) treated with laminates?
Staining and pits resulting from developmental enamel defects can be covered with a porcelain surface after a fine polishing procedure, thus improving aesthetics and isolating these areas prone to decay from bacterial plaque.
14. Does color change occur after the application of porcelain laminates?
Since glass ceramic materials are glazed at high temperatures in the laboratory, they do not exhibit structural staining or yellowing due to factors like coffee or tobacco, because their surfaces are made smooth.
15. Can the result be predicted in accordance with Europadent standards?
In the planning phase, virtual designs are created and applied to your mouth with temporary acrylic materials (using the Mock-Up technique) before any procedure is performed on your tooth; this way, you can physically see the result in front of a mirror.







