

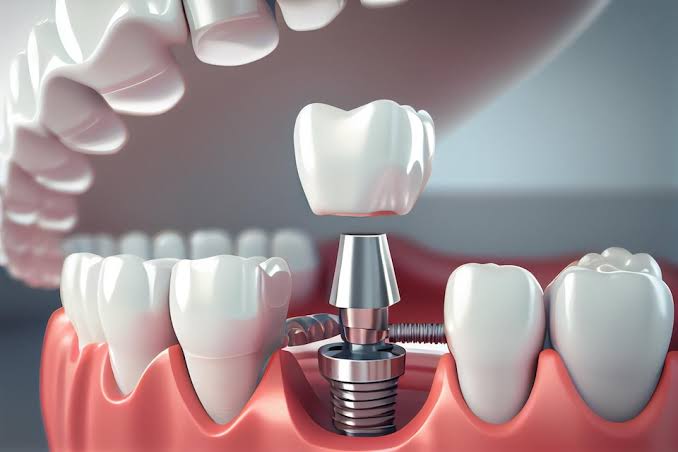
Can dental calculus cleaning be done after implant treatment?
After implant treatment, dental calculus cleaning is not only possible but also a professional oral care procedure that must be regularly performed to protect the health of the surrounding tissue. Hardened tartar (calculus) deposits that accumulate over time on the prostheses placed on titanium materials embedded in the jawbone and at the gum line can be safely removed from the tissues without damaging the surfaces using specialized medical instruments in a clinical setting.
One of the common misconceptions that patients have after the treatment of tooth deficiencies is the belief that non-functional porcelain or titanium structures do not require cleaning and professional care. However, the oral cavity is a dynamic flora where minerals and bacteria in the saliva are in constant interaction. Just like in natural teeth, in the areas around artificial roots where brushing is insufficient, bacterial plaque accumulates in blind spots and calcifies over time. These stones are the primary source of infections. The long-term biological compatibility of the structures embedded in the jawbone can only be sustained by the regular professional cleaning of these dental tartars under clinical supervision.
Why is Professional Cleaning (Ultrasonic Scaling) Important After Implant Treatment in Izmir?
Professional cleaning after treatments applied in İzmir is vitally important to prevent anaerobic bacteria in dental calculus, which can’t be removed with mechanical brushing at home, from causing inflammation in the gums (mucositis) and eroding the jawbone (peri-implantitis). The long-term functional preservation of medical titanium surfaces and the porcelain teeth above them is directly dependent on the removal of bacterial plaque from the oral flora with this professional support.
During patient follow-ups in Avrupadent clinics located in İzmir, the most emphasized topic is keeping the newly created chewing system clean. When dental calculus accumulates around natural teeth, the rich connective tissue surrounding the blood vessels may combat these bacteria for a while. However, there is no protective connective tissue around artificial roots; the material is in direct contact with bone cells. This anatomical disadvantage causes even the smallest dental calculus or plaque formed to reach the jawbone much faster than a natural tooth, leading to infections. Professional cleaning (detartrage) is the only medical barrier that stops this quick dissolution before it even begins.
Why Can’t the Tools Used in Natural Tooth Cleaning Be Used in This Process?
The hard stainless steel tools (scalers) and high-frequency devices used in natural tooth cleaning cannot be used in this process because they may scratch the titanium body’s smooth neck and the glaze layer of porcelain. Because scratched microscopic surfaces will create protected areas for bacteria to cling, only special tools made of carbon, Teflon, plastic, or pure titanium that do not damage the material are preferred for tooth calculus cleaning.
The surface of dental implants is the hardest tissue in the human body and shows high resistance to scratches when cleaned with traditional metal dental instruments. However, the surfaces of prosthetics that are placed in the mouth after being polished in a laboratory environment, and particularly the titanium abutment pieces that remain under the gum, are quite sensitive to metal scratches. If these surfaces are interfered with using a standard cleaning tool, the microscale smoothness of the surface will be disrupted. The microscopic cracks (scratches) that open on the surface will eventually turn into safe havens where bacteria can enter and hide over time. In light of this medical fact, the cleaning process is carried out with special equipment suitable for the material’s physics.
| Equipment / Method | Usage for Natural Teeth | Usage for Titanium and Prosthetic Surfaces |
|---|---|---|
| Manual Hand Tools (Scalers) | Tools with hard tips made of stainless steel. | Non-scratching tools made of carbon, teflon, or special plastic alloys. |
| Ultrasonic Cleaners | With hard metal tips, standard or high-frequency vibrations. | With tips covered in silicon rubber, much lower and more precise vibration frequencies. |
| Polishing Paste | Standard particulate, fluoride-containing stain removers. | Extra fine pastes that do not abrade the glassy surface of porcelain, with a very low RDA value. |
Is Tartar Buildup on Titanium and Porcelain Surfaces Different from Natural Teeth?
Tartar buildup on titanium and porcelain surfaces occurs in the same way biochemically as in natural teeth, through the deposition of calcium and phosphate minerals from saliva onto soft bacterial plaque; however, the design contours of these artificial materials (especially beneath bridges) harbor more “blind spots” compared to natural teeth, leading to greater retention of food debris and consequently faster tartar formation.
No matter how smooth and polished porcelain crowns or zirconium coatings are produced, within seconds of first contact in the oral environment, a transparent film layer called “pellicle” forms on their surfaces. Bacteria begin to adhere to this film and start to create plaque (biofilm). If this plaque is not removed within 48 hours through brushing or other cleaning methods, the saliva will carry this plaque. In cases of complete edentulousness, due to insufficient natural mechanical cleansing (movement of the tongue and cheeks) at the junctions of the anterior regions where the pink acrylic thickened prostheses meet the gums, tartar formation is a quite common clinical finding.
What Medical Issues Can Arise if Tartar Around the Implant is Not Cleaned?
If tartar around the implant is not cleaned, the bacteria proliferating on the porous surface of the tartar primarily cause inflammation by reddening the gums (mucositis), and subsequently, this inflammation can spread to the jawbone, leading to the resorption of bone tissue in a crater-like manner (peri-implantitis). Progressive bone resorption concludes with the medical material losing its mechanical support in the jaw, necessitating advanced surgical interventions that would require the removal of the structure from the body.
Dental calculus is not just a simple aesthetic flaw; it is an active infection site. Patients often postpone cleaning their calculus by saying, “I don’t have pain, there’s no problem.” However, since there is no nerve network around the titanium root as there is in the tooth, the infection does not cause any pain or swelling while it erodes the bone. This is the most dangerous and insidious aspect of the disease. The only external sign of this destruction is a small bleeding from the gum while brushing. The growth of calculus into the gum pocket tears the mechanical seal created by the gum with the prosthesis, allowing bacteria to directly flow into the jawbone. The resorption of the bone escaping this acidic bacterial environment is the primary reason for treatment failure.
- Mucositis (Early Stage): This is simply the redness, swelling of the soft tissue (gum), and bleeding while brushing. It fully recedes with cleaning.
- Peri-Implantitis (Advanced Stage): This is when the infection reaches the jawbone. Radiographs show vertical erosion of the bone.
- Mobility (Loosening): This indicates that the structure has started to move mechanically after losing bony support, signifying irreversible tissue damage.
- Halitosis (Bad Breath): This is an stubborn unpleasant odor associated with the gases produced by anaerobic bacteria in dental calculus.
What Procedural Steps Does Implant Tooth Calculus Cleaning Involve in a Clinical Setting?
Dental tartar cleaning in a clinical environment involves the dentist detecting accumulation points using special equipment (loupes) or intraoral cameras, carefully removing the tartar from beneath the gum tissue with carbon or Teflon hand instruments, rinsing microscopic plaques with low-frequency ultrasonic devices, and finally applying a professional polish using special pastes on porcelain surfaces.
The detartrage procedure is an extremely meticulous clinical protocol. When the dentist begins the examination, they first place millimetric periodontal probes (measuring instruments) into the gap between the prosthesis and the gum to measure the depth of the pocket and the bleeding index. Areas with bleeding indicate that tartar is harbored beneath the gum tissue (subgingival) even if it is not visible. Special Teflon curettes gently slide into the gum pocket, and the material that has formed into a tartar mass is physically dislodged and removed. The water jets from ultrasonic instruments simultaneously wash and disinfect the area. The polishing applied in the final phase is essential to restore cleaned but possibly slightly dulled porcelain surfaces back to a slippery and plaque-resistant (bacteria-repelling) physical structure.
How Often Should the Detartrage Procedure Be Scheduled at İzmir Avrupadent Clinics?
At İzmir Avrupadent clinics, the detartrage (dental tartar cleaning) procedure should generally be scheduled at six-month or yearly periodic examinations, depending on the patient’s individual oral hygiene habits, tooth structure, and systemic health condition. In these medical processes requiring regular dentist follow-up, tartar is proactively cleaned in a clinical environment before it reaches a level that could damage tissue (dissolve bone).
The understanding of preventive dentistry adopted in the processes of Avrupadent, which operates in the Izmir location, aims to stop the emergence of issues at their source rather than waiting for them to arise. The calcium levels in the dental structure of some patients are genetically much higher (the pH of their saliva is alkaline); these individuals are more prone to the formation of dental calculus even if they maintain excellent oral hygiene. Additionally, patients who smoke or have uncontrolled diabetes also experience this process more rapidly. Therefore, the standard six-month control periods are personalized by drawing them to shorter intervals, such as four or three months, based on the medical evaluations performed by the dentist.
Does At-Home Oral Care Substitute for Clinical Dental Calculus Cleaning?
While at-home oral care is essential for removing soft bacterial plaque (biofilm), it can never substitute for clinical dental calculus cleaning because it cannot physically remove hardened and mineralized (calcified) dental calculus due to the effects of the buildup, and home care cannot adequately reach the blind spots under the gums of prosthetics. Home care and clinical debridement are not alternatives to each other; they are complementary health measures.
Brushing teeth twice a day with the right technique, using an interdental brush and mouth rinse, incredibly slows down the formation of tartar but cannot completely prevent it. This is because the back (tongue-facing) surfaces of teeth or the undersides of multiple bridges are anatomical blind spots that cannot be perfectly cleaned with human hand skills. If soft plaque stays on the tooth surface for about 48 hours, it begins to calcify due to the sedimentation of ions in the saliva. Once tartar forms, the strength of toothbrush bristles isn’t enough to displace this hard calculus. Patients staying away from the clinic with the thought of “I brush regularly every day, I don’t need cleaning” causes the accumulation of subgingival (below the gum line) tartar over the years, silently eroding the jawbone.
| Comparison Criteria | Home Type Individual Mouth Care | Professional Detailing in Clinical Environment |
|---|---|---|
| Intervention Type | Soft bacterial plaque (Biofilm) and food residues. | Hardened, mineralized tooth tartar (Tartar/Calculus). |
| Accessible Areas | The outer surfaces and upper parts of the gum margins of the dentures. | The insides of gum pockets (Subgingival), blind spots, and underneath the denture surfaces. |
| Frequency of Application | At least 2 or 3 times a day, regular and mechanical cleaning. | According to the physician’s recommendation, usually once every 6 months or once a year. |
How Do Systemic Diseases (Diabetes, etc.) Affect Tartar Formation?
Systemic diseases, especially diabetes, create conditions that allow bacteria to multiply rapidly by increasing sugar levels in the blood and saliva, and since they disrupt tissue perfusion, even the smallest dental stone can significantly accelerate the risk of infection and destruction (bone resorption) compared to healthy individuals. Individuals with this disease must follow their clinical cleaning appointments much more frequently as a medical necessity.
The formation of dental stones is related not only to the foods we eat but also directly to the chemical content of the fluids secreted by our salivary glands. In diabetic patients, fluctuations in blood sugar slow down the function of the salivary glands, leading to dry mouth (xerostomia). When saliva decreases, the mouth’s self-cleaning (mechanical cleaning) capability declines, allowing plaque to adhere to prosthetic surfaces much more rapidly. Furthermore, the immune cells of diabetic patients reach infection areas (due to capillary damage) more slowly, making it difficult for the gum tissue to oppose these stones, leading to rapid withdrawal. This biological picture underscores the importance of preventive dentistry in individuals with systemic diseases.
How Do Tobacco Products Accelerate Tartar Buildup Around Implants?
Tobacco products slow down the salivary flow in the mouth and dry out the tissue, making it much easier for bacteria to adhere to porcelain surfaces, while the heat effect created by smoke accelerates the deposition of calcium in saliva, physically increasing tartar buildup. Additionally, nicotine narrows capillaries, masking the bleeding signs of gum inflammation (the body’s alarm system) and allowing infections to progress insidiously.
The main reason patients who smoke are always in a high-risk group for dental surgery is that tobacco smoke completely alters the composition of the oral flora in favor of anaerobic bacteria. Anaerobic bacteria that promote the formation of tartar proliferate much more aggressively in oxygen-depleted environments created by tobacco smoke. Furthermore, the tar and other chemicals found in tobacco products create an aesthetic disaster by turning tartar dark brown or black. Patients do not notice bleeding when brushing because smoking constricts the blood vessels in the gums, and they cannot detect the advancing deep tissue damage under the tartar masses. Quitting tobacco use is one of the most critical parts of maintaining the health of the jawbone for many years.
What Should Be Considered in Oral Care After Professional Tartar Cleaning?
In oral care after professional tartar cleaning, attention should be paid to the technique of brushing teeth with gentle circular movements at a 45-degree angle to the gum (modified Bass technique), the consistent use of special thick dental threads (superfloss) for the spaces under bridges, interdental brushes, and pressure-sensitive oral brushes. To extend the protective effect of the medical cleaning, it is essential to strictly adhere to the care routines recommended by an Implantology specialist.







