

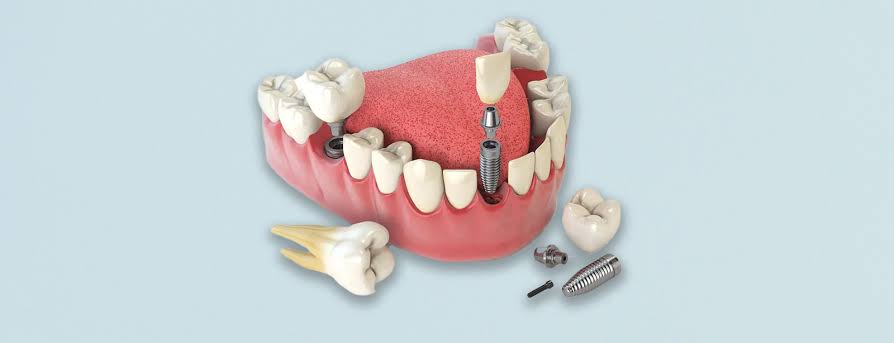
How is Implant Treatment Planned for Single Tooth Deficiency?
The overall functioning of the chewing system inside the mouth is established on the balance of forces transmitted by each tooth to each other and to the jawbone. A loss of a single tooth, which may occur due to various traumas, advanced fractures, or periodontal tissue diseases, not only creates a local gap in that area; it also leads to a medical condition that causes chain reactions in the biomechanical structure of the entire chewing mechanism. The treatment procedures applied to fill this gap through medical means and restore physiological functions in their original form require detailed clinical planning.
In modern dental approaches, the principle of minimal intervention to existing healthy tissues is adopted. In this context, creating a structure supported by the jawbone in only the missing area, without intervening in the healthy teeth on both sides of the gap, emerges as a medical strategy. These restorative processes, realized by taking advantage of the compatibility of titanium materials with human physiology, are individually tailored according to the patient’s jaw anatomy, bone density, and soft tissue parameters. In the following sections, the clinical steps applied in cases of single tooth deficiencies, the radiological assessments, and the biological integration processes will be addressed in detail.
What Changes in Jaw Anatomy When a Tooth is Lost?
When a tooth is lost, the chewing pressure transmitted to the jawbone in that area disappears, leading to volume decreases in the bone tissue. The teeth on both sides of the gap remain unsupported and begin to tilt towards that area. The opposing tooth in the opposite jaw extends towards the gap, thereby altering the closure balance.
Anatomical changes begin at the cellular level. The tooth root is connected to the surrounding alveolar bone socket by fine fibers called “periodontal ligament.” The force generated during chewing is transmitted to the bone through these fibers, stimulating bone-building cells (osteoblasts). When a tooth is extracted, this mechanical stimulus is interrupted, leading the bone tissue to enter a physiological remodeling process, gradually losing volume. This condition is referred to as atrophy or resorption. Particularly in the first months following extraction, significant changes in the bone’s width and height are observed.
Another major change in jaw anatomy is observed in neighboring teeth. Due to their structure, teeth are arranged in a way that they support each other. When a unit is removed, adjacent teeth tilt toward the gap (mesialization/distalization) and lose their contact points. The disruption of contact points prepares the ground for food to get trapped in between, subsequently increasing the risk of decay in those areas. Additionally, the tooth directly opposite the gap (in the upper or lower jaw) cannot find a surface to make contact and enters a growth equilibrium downward or upward, negatively affecting joint balance.
What Needs Does Implantology Address in Closing Single Tooth Gaps?
In closing single tooth gaps, implantology eliminates the need to intervene with neighboring teeth by placing an artificial titanium unit in place of the lost root. It responds to essential medical needs such as restoring chewing function transmitted to the jawbone and preventing anatomical erosion while ensuring aesthetic integrity.
The fundamental response to this medical application is the principle of “tissue preservation.” The transmission of chewing force directly to the jawbone through an artificial root ensures the continuation of physiological stimulation in that area. The stimulated bone tissue tends to remain active and maintain its volume. This titanium structure, which mimics the tooth root, also acts as a physical barrier against the neighboring teeth, which are prone to displacement into the gap, stabilizing the existing position of the dental alignment.
In addition to functional needs, phonetic and aesthetic concerns are also managed within this planning. In the case of single tooth losses in the anterior area, the inability to accurately pronounce sounds and the gap created in the smile line can affect the person’s social life. The crown structure that rises from within the jawbone with a natural tooth form supports speech functions by regulating airflow. It maintains the occlusal plane within physiological limits by preventing the opposing tooth from over-erupting.
What is the Role of Neighboring Teeth in Single Tooth Implant Planning?
In single tooth implant planning, the root openings, gum levels, and overall health conditions of neighboring teeth directly determine the position of the titanium screw to be placed. To avoid damaging the roots of neighboring teeth, millimetric distances are calculated, and it is aimed that the new crown forms compatible contact points with these teeth.
In three-dimensional radiological scans (Dental Tomography) taken before the surgical intervention, the root structures of the teeth located on the right and left of the gap are examined in detail. In cases where roots are angled towards the gap, it is medically necessary for the titanium screw to be placed in between not to contact these roots. According to standard medical protocols, a certain amount of healthy bone tissue (generally at least 1.5 – 2 millimeters) should be left between the implant surface and the root of the neighboring natural tooth. This distance is critical to protect the vitality of the neighboring tooth during the operation and to ensure the continuity of blood circulation in that area.
In addition, the shapes of the crowns on adjacent teeth determine the dimensions of the porcelain structure to be created. The dentist calculates the triangular spaces in areas where the teeth connect to the gums, known as the “embrasure”. The contact that the new tooth will establish with neighboring teeth must be adjusted with medical precision that will prevent food residue from getting trapped but still allow for the use of dental floss. If there is tooth decay or gum inflammation in the neighboring teeth, the process includes performing periodontal or endodontic (root canal) treatments on these teeth to rid the surrounding tissue of infection before the surgical procedure.
How is Aesthetic Analysis Managed for Single Tooth Losses in the Anterior Zone?
Aesthetic analysis for single tooth losses in the anterior zone is managed through digital software, taking into account the lip outline, gum tissue symmetry, and the color translucency of adjacent teeth. The goal is to preserve the shape of the soft tissue on the smile line, and the neck of the titanium root is positioned at a depth that aligns with the anatomical structure of the gum tissue.
During the smile, the management of aesthetic expectations, alongside biomechanical durability, is a primary planning criterion for the visible anterior gaps. The dentist analyzes lip support and the appearance of the teeth at rest using clinical photographs and optical intraoral scanners. It is aimed that the “Zenith point”, known as the peak point of the gum, is located on a symmetric line with neighboring natural teeth. To establish this symmetry, the emergence profile of the titanium material implanted into the jawbone must be adjusted so that the porcelain crown does not show an outward or inward flare.
The “gingival biotype” referred to in aesthetic area planning is very important. In cases where the tissue is thin and translucent, the gray reflection of the underlying metallic titanium structure may be noticeable from the outside. If this situation is anticipated as part of the aesthetic analysis, the step of transferring a thin soft tissue (connective tissue graft) taken from the patient’s palate to the relevant area can be added to the surgical procedure. In this way, by thickening the gum tissue, both the color reflection is prevented, and a biological defense line is created against potential tissue retraction that may occur over time.
How is the chewing load calculated in single tooth deficiencies in the posterior region?
In single tooth deficiencies in the posterior region, the chewing load is calculated in conjunction with radiological data based on the relationship of the jaw closure and the muscle strength of the patient. Since vertical and horizontal forces are intense in these areas where molar teeth are present, wide-diameter titanium screws are selected to distribute the force to the bone.
The molar teeth that form the back part of the chewing system are exposed to high mechanical pressures created by the facial muscles (particularly the masseter muscle) during the occlusion process. In the absence of the first or second large molar tooth, the planning to be done for that area diverges from the aesthetic-focused planning in the anterior region, shifting towards the axis of biomechanical durability. The dentist examines how the patient closes their jaw, whether they have a teeth grinding (bruxism) habit, and the anatomical structure of the opposing tooth.
Based on these calculations, the structure of the material to be placed in the background is determined. The roots of the small teeth are left intact in natural anatomy. To withstand this pressure and support the broad surface porcelain tooth that will come on top, expanded (thick) models are included in the planning, to the extent that bone volume permits. To prevent forces from concentrating at a single point and causing damage to the jawbone, the angle of implant placement is adjusted through medical software to directly transmit the vertical forces exerted during closing to the center of the bone.
What Biological Processes is the Individual Treatment Calendar Based On?
The individual treatment calendar is determined according to the cellular renewal rate in the patient’s jawbone, bone density, and the extent of the surgery performed. The biological process during which titanium surfaces are surrounded by bone cells is the main criterion; this process can vary between a few months depending on the person’s metabolic condition.
After the surgical intervention, the body initiates a tissue repair process in the area. This process, referred to as “osseointegration,” signifies osteoblast (bone-forming) cells progressing towards the micro-pores on the titanium surface and establishing new bone tissue there. Since the mandible has a more compact and rigid structure anatomically, cellular retention here can develop earlier, and the prosthetic phase (the layering process) can typically proceed after a waiting period of two or three months.
The upper jawbone has an anatomy characterized by a sponge-like (cancellous) structure, which leads to variability in its vascularization and requires more time for cellular maturation. In the upper jaw, the treatment schedule can extend up to a range of three to six months. Another factor that prolongs the schedule is additional surgical procedures. If the jawbone in the area of tooth loss has resorbed, and bone grafting has been done with titanium screws in the same session, an extra biological maturation period is added to the schedule for the added particles to integrate with the patient’s own bone.
What Determines the Diameter of the Titanium Root Used in Single Tooth Implantation?
The diameter of the titanium root is determined according to the anatomical size of the missing tooth, the thickness of the existing bone, and the distance between neighboring tooth roots. For example, a narrower structure is planned for a lower incisor, while wider forms are preferred in the area of a molar to meet increased chewing pressure.
Diameter selection begins with a clinical measurement known as area analysis. The physician calculates the mesiodistal width of the space where the tooth is missing and the buccolingual thickness in the cheek-tongue direction. The material to be chosen should be thin enough to leave a healthy bone wall that will provide adequate vascularization around it, but thick enough to withstand the occlusal (chewing) forces applied to it.
The table below summarizes the medically planned diameter strategies according to the group of the missing tooth in single tooth losses, along with the anatomical justifications of these strategies at a general level:
| Group of Missing Teeth | Preferred Structural Diameter | Anatomical and Biomechanical Justification |
|---|---|---|
| Lower Jaw Anterior Incisors | Narrow Diameter (e.g., 3.0 mm – 3.5 mm) | The neighboring tooth roots being very close to each other and the anatomical structure of bone thickness in that area being inherently thin. |
| Upper and Lower Jaw Molars / Small Molars | Standard Width (Example: 3.5 mm – 4.2 mm) | The presence of a bone volume that will support the aesthetic profile and counteract standard chewing/fracture forces. |
| Upper and Lower Jaw Big Molars | Wide Width (Example: 4.5 mm – 6.0 mm) | The need to absorb the high pressures coming from the masseter muscle and to mechanically support wide porcelain crowns. |
How Does the Process Progress in Singular Spaces Where the Gum Has Been Pulled?
The process in singular spaces where the gum has been pulled progresses with the planning of additional periodontal surgical steps aimed at increasing the volume of soft tissue. Methods such as connective tissue transfers help to thicken the gum, preventing the formation of gray reflections on the neck part of the titanium screw to be placed and supporting the aesthetic profile.
If a long time has passed since the tooth extraction, the gum covering the jawbone in that area also loses volume and flattens. When material is directly placed in an area where soft tissue is insufficient and a covering is done on it, the gum crown cannot sufficiently cover it, leading to the formation of spaces where “food retention” (accumulation of food remnants) may occur. In addition, the presence of a thick and dense gum tissue called “keratinized” around the titanium for its protection acts as a biological barrier, limiting the bone’s exposure to infections.
Depending on this medical need, soft tissue grafting may be included in surgical planning. While the flap (removal of the gum tissue) procedure is performed in the relevant area, a small piece of connective tissue or epithelial tissue is taken from the patient’s palate and placed under the thinned gum. This tissue transfer ensures the formation of a healthy mucosal structure that closely surrounds the implant neck by increasing the volume of the area. The shaping of the soft tissue is a carefully awaited healing period before transitioning to the prosthesis (crown) stage.
What Are the Structural Differences Between Traditional Bridges and Single Implants?
Traditional bridges operate on the principle of being supported by the adjacent healthy teeth, while single implants fill the gap by relying on the jawbone independently. Structurally, one is a connected system that puts pressure on neighboring tissues, while the other is a singular unit that mimics natural tooth anatomy.
In clinical planning, the restoration method to be applied is evaluated according to the patient’s existing edentulous condition and anatomical constraints. The fundamental difference of implantology practices in the medical literature is that it transfers the chewing dynamics directly to the underlying bone instead of to the surrounding tissues. The biomechanical effects and clinical operational differences of both treatment approaches are compared in the table below:
| Comparison Criteria | Single Tooth Implant Supported Crowns | Traditional Three-Unit Bridge Systems |
|---|---|---|
| Effect on Neighboring Teeth | The healthy teeth adjacent to the gap are not touched, and their enamel and structures remain intact. | The supporting teeth on both sides of the gap are prepared at the enamel level to form the feet of the bridge. |
| Effect on Jawbone | By applying mechanical pressure, it slows down the physiological stimulation and the resorption (melting) process of the bone. | Because the load does not directly go to the bone in the area with a missing tooth, anatomical melting may occur in that area. |
| Oral Hygiene | Because it is a singular unit, it can be easily cleaned from the sides with standard dental floss and a toothbrush. | Since the teeth are connected (blocked), special brushes or flosses under the bridge should be used for inter-cleaning. |
| Medical Timeline | The cellular bone healing (osseointegration) is spread over a timeline lasting several months as expected. | Since there is no surgical stage, measurements and laboratory procedures are completed within a few weeks, and the prosthesis is delivered. |
How Does Healing Function in Single Tooth Restorations?
The healing function provides a natural tooth emergence form by placing components on a titanium screw that completes the intra-bone healing. This cylindrical piece allows the gum to gain a rounded contour, effectively surrounding the porcelain tooth that will be added on top, like an aesthetic frame.
In the initial surgical phase, when the titanium root is placed in the jawbone, it can be completely covered with gum tissue and stitched for protection against infections. After the bone healing confirmed over several months, a small local intervention is done to reopen the gum before proceeding to the prosthetic phase, during which the upper part of the titanium is attached with a metallic healing cap called “gingiva former.” These small devices are usually held in the mouth for 7 to 14 days.
The medical purpose of this waiting period is to change the flat form of the gum tissue in order to create an internal cavity (in the shape of a cup). As the gum heals around this connection, the crown tooth prepared in the laboratory fits perfectly into this cavity. Thus, a natural anatomical tooth eruption visual is obtained from within the gum, and potential gaps where food debris could accumulate along the gum margin are structurally closed.
What Factors Are Considered When Choosing Crown (Restoration) Material?
When choosing crown material, the position of the gap within the mouth, the structure of opposing teeth, and the patient’s occlusion habits are taken into account. In anterior regions, materials with high light transmittance come to the forefront, while in posterior areas, high mechanical strength alloys are evaluated with the goal of achieving aesthetic and functional integrity.
In single tooth deficiencies, after a titanium root is established as a foundation, different dental laboratory materials are planned for the occlusal surface (crown) visible within the mouth. Materials such as “zirconium” or all-ceramic types are frequently preferred for anterior incisors included in the smile line. The white foundation of zirconium draws a profile very similar to the light reflection and breaking characteristics of natural tooth enamel, so matte or dark reflections visible at the gum margin do not occur with this material in metal-supported porcelains.
When it comes to posterior molars, the mechanical stresses created by occlusal forces come into play. In these areas, ceramics (porcelains) with metal infrastructure that have high breaking resistance or monolithic (one-piece) zirconium blocks are prioritized in planning over aesthetics. If the patient has a tendency to grind their teeth at night, the selection of dental materials with suitable hardness that will not engage in abrasive interaction with the enamel of the opposing tooth and can tolerate the pressure is made by the physician based on clinical data.
How is Process Management Optimized in Corporate Clinical Operations?
Process management in corporate clinical operations is optimized through the use of digital scanning technologies, implementation of infection control protocols, and multidisciplinary physician evaluations. Similar to what is observed in Avrupadent processes, each step, from radiological analyses to laboratory phases, is recorded within the framework of medical standards for case follow-up.
From the first step of planning to the last session where the crown is placed, the flow of procedures in medical service centers is based on specific quality standards. To prepare the oral flora for surgical procedures, periodontal (gum) examinations are performed to minimize infection risk. All drills and hand instruments to be used surgically undergo autoclave sterilization cycles to prevent cross-contamination. The patient’s medical history is entered into the system, allowing coordination with physicians regarding the systemic medications used and potential allergic conditions.
Integration of digital dentistry plays a significant role in optimizing these processes. Implantology applications involve virtual surgical planning based on three-dimensional tomographies of the jaws, calculating millimetric adjustments. During the measurement phase, data is transmitted to dental technicians digitally using intraoral scanners instead of traditional materials. This corporate operational structure supports medical predictability by minimizing human resource deviations during the operation.
What are the Frequently Asked Questions?







