

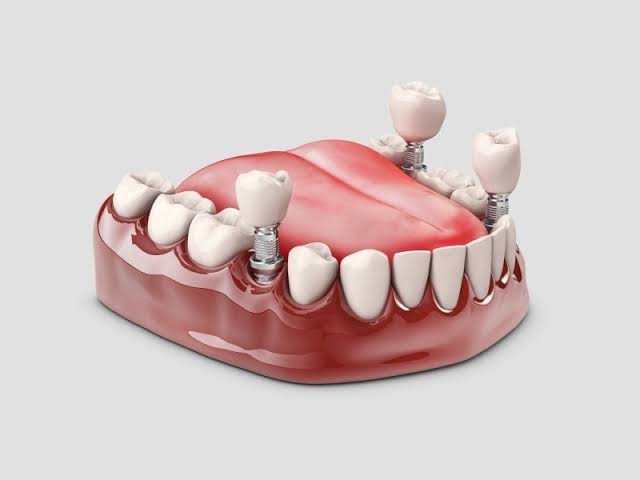
Is Gum Treatment Required Before Implant Placement?
Titanium root applications placed in the jawbone to compensate for dental deficiencies are advanced medical procedures that directly interact with the biological ecosystem of the oral cavity. The ability of an artificial material to integrate at the cellular level with human tissue (osseointegration) depends on the surgical area being free of microbial agents and the surrounding tissues having a healthy capacity for repair.
What is the Necessity of Gum Treatment Before Implant Placement and Its Role in Medical Planning?
The fundamental principle in jaw surgery is to convert the surgical area into a sterile (or minimally microbial burdened) environment. The oral cavity hosts billions of bacteria. Gum diseases develop as a result of these bacteria colonizing the area between the tooth and the mucosa (biofilm). When the physician makes an incision in the gum to place the titanium screw, the pathogenic bacteria in that area find an opportunity to directly invade the jawbone and the wound site.
In clinical planning, surgical procedures are always postponed to allow for infection control. This is because the repair mechanisms of cells are not activated in inflamed tissues, but rather the mechanisms of the immune system battling bacteria are active. Placing material under the bleeding, swollen, and bruised gum tissue forces the cells to surround the titanium surface. For this reason, the existing inflammation is first cleared through medical means, allowing the tissue to regain its physiological color and consistency; then the surgical stage is initiated.
Can Surgical Procedures Be Performed in the Presence of Active Gum Inflammation (Periodontitis)?
Periodontitis is a destructive disease that dissolves not only the visible gum tissue but also the underlying periodontal attachments (fibers connecting the tooth to the bone) and the alveolar bone itself. The microorganisms causing this disease (especially anaerobic bacteria such as Porphyromonas gingivalis) exhibit extremely aggressive spreading patterns. During the period when the disease is active, the immune system sends a significant number of inflammatory cells (macrophages, neutrophils) to the area.
If this destructive environment is not treated, and the jawbone is opened solely for the purpose of placing a missing tooth by positioning a titanium root, the existing pathogenic bacteria can easily adhere to the surface of the newly placed material. This situation initiates a chronic tissue destruction known as “peri-implantitis” which rapidly dissolves the bone surrounding the artificial root. Medical organizations primarily aim to clear all inflammatory foci in the mouth through periodontology specialists to mitigate this risk.
What Medical Purpose is Performed Before Dental Calculus Cleaning (Detartrage) Operation?
Dental calculi (calculus) form as a result of the binding of calcium ions in saliva with bacterial plaque, hardening over time. Due to their rough surfaces, they continually attract new bacteria. The areas where dental calculus is present constantly irritate the gums; this irritation leads to swelling (edema) of the gums, redness, and bleeding at the slightest touch.
| Medical Parameters | Condition Before Cleaning (Presence of Calculus) | Preparation Stage After Cleaning |
|---|---|---|
| Tissue Bleeding | Uncontrolled bleeding associated with inflammation narrows the surgeon’s field of view during the operation. | Tissue with reduced edema experiences only normal levels of physiological bleeding during the surgical incision. |
| Bacterial Load | Millions of pathogenic bacteria wait on the stones to migrate to the wound site. | The bacterial population is restricted, and wound repair cells focus on organizing around titanium rather than fighting off bacteria. |
| Stitch (Suture) Retention | Swollen and inflamed (loose) tissue struggles to hold the stitches placed after surgery, and the wound may open. | The thick (fibrotic) form of the mucosa ensures that the wound epithelializes (closes) without issues, maintaining the stability of the stitches. |
How are Gum Diseases Diagnosed in Clinics in İzmir?
Before jaw surgery, creating a medical map of the patient is not a procedure that can be completed with just visual examination. The extent of inflammation and how much it affects the teeth or jawbone is measured using special medical devices. Dentists gently slide instruments known as periodontal probes, which have millimeter markings, into the sulcus (the space between the tooth and gum) between the teeth and gums.
In a healthy anatomy, the depth of this sulcus should be between 1 to 3 millimeters. If the probe goes down to 4 millimeters or deeper, it indicates the formation of a pathological “pocket”. This means that bacteria have started to thrive in these deep pockets in an anaerobic environment, beginning to dissolve the bone. Observing bleeding during probing (BOP – Bleeding on Probing) during clinical assessment is the most concrete physiological indication of active inflammation in that area. When combined with radiological images taken simultaneously, this data is used to determine the schedule for the patient’s surgical operation preparation.
How is Gum Preparation Conducted Before Surgical Operations within Avrupadent?
The most characteristic feature of institutional approaches in dentistry is their consideration of the patient’s oral anatomy as a whole. While focusing on the replacement of a missing tooth, the potential for infection in adjacent teeth to disrupt this process cannot be overlooked. Stabilizing the patient’s oral flora before the surgical procedure is planned by the medical boards’ mutual clinical decision.
- Elimination Phase: Teeth roots that have lost bone support and are infected (loose) are extracted and removed from the mouth.
- Hygiene Phase: Supra-gingival (above the gum line) and sub-gingival (below the gum line) tartar is removed using ultrasonic instruments; patient-specific brushing techniques are taught.
- Evaluation Phase: The physiological response of the tissue is measured two to four weeks after cleaning. If the gums have returned to a pink and firm form, the oral surgeon will initiate the operation schedule.
When is Root Surface Leveling (Curettage) Planned for Anatomical Conditions?
Tooth stone cleaning generally targets the crown part visible from the outside of the tooth and the immediate gum line. However, as the disease progresses, bacteria and hardened calculus layers descend into the deep, visually inaccessible areas of the tooth root. These deposits that form on the root surface cause the root to become porous and toxic.
The dentist removes calculus and bacterial toxins from the root surface by directing fine-tipped medical curettes into these deep pockets under local anesthesia (Scaling and Root Planing). The goal is to make the root surface as smooth as glass. A smooth surface prompts the gum tissue to regenerate healthily, attempting to close that pathological pocket. Without this deep cleaning, placing a titanium screw near a nearby jawbone increases the risk of infection from a medical perspective.
Is Gum Recession a Barrier for Titanium Root Applications?
The mucosa inside the mouth exists in two different forms: The first is the “alveolar mucosa”, which is flexible, thin, and mobile, covering the inside of our cheeks; the second is the “keratinized gingiva”, which is thick, immobile, and tightly surrounds the teeth, designed to withstand chewing forces. It is expected that titanium artificial roots will be completely surrounded by this thick and protective keratinized gum tissue just like natural teeth.
If there is advanced gum tissue retraction in the area, it means that this protective band has melted away, and flexible alveolar mucosa has come in its place. The flexible mucosa allows bacterial plaque to seep into the neck area of the titanium screw since it can easily shift during brushing or chewing. Moreover, aesthetically, the gray reflection of the titanium can shine through the gum tissue. When doctors identify this deficiency while evaluating the tissue map, they take additional medical measures aimed at thickening the tissue in that area.
What is the Purpose of Soft Tissue Graft (Gum Grafting) Surgery?
Just like the bone powder (hard tissue) surgeries applied to increase the jawbone, soft tissue surgeries are also performed to increase the gum tissue. The neck region where the titanium screw opens to the oral environment is the most sensitive transition point. The thickness of the gum around this neck (biotype) acts as an anatomical fortress that makes it difficult for bacteria to reach the bone.
The upper gum is the area where keratinized connective tissue is most abundant in human anatomy. The doctor microsurgically transplants a small piece of tissue taken from the gum to the area where titanium will be placed, which has thin gum tissue. The body vascularizes this tissue within a few weeks, turning it into its own piece in that region. Thickened gum tissue not only increases biological defense but also greatly contributes to the artificial crown appearing in a natural tooth form aesthetically.
How Long Should One Wait to Transition to Surgical Phase After Periodontal Healing?
In medical procedures, timing must respect the body’s repair physiology. When the treatment of gum diseases is completed, it does not mean that the tissue has regained its old resistance at the moment the inflammation disappears. It takes time for the inflammatory cells to leave the area and for repair cells known as fibroblasts to arrive, for new vascular structures to be formed, and for the connective tissue to take a dense (fibrotic) form.
| Performed Medical Procedure | Average Waiting Period | Physiological Justification for Waiting |
|---|---|---|
| Standard Detartation (Surface Cleaning) | 7 – 14 Days | Resolution of temporary edema on the mucosal surface and return of local bleeding to normal limits. |
| Deep Rooting (Root Surface Regulation) | 3 – 4 Weeks | Completion of the organization of the connective tissue within the pockets to bond to the root surface (reattachment). |
| Soft Tissue Graft (Palate Transplant) | 6 – 8 Weeks | Complete vascularization (vascularization) of the transplanted tissue in the new area and adaptation of the cells to the region. |
What are the Effects of Systemic Diseases on Gum Health and Surgical Preparation Process?
The oral cavity is not an isolated area from the body’s systemic health. Biochemical fluctuations in the blood directly cause reactions in the gum mucosa. Especially in cases of uncontrolled diabetes, high circulating glucose molecules in the blood can combine with proteins (glycation) and damage cell walls. This situation limits the mobility of the defense cells in the gums, leaving the tissue defenseless against bacteria.
Gum diseases progress much faster in individuals with diabetes, and when surgical procedures (incisions) are performed, the healing of the wound is delayed compared to non-diabetic patients. Therefore, during the surgical preparation phase, individuals with systemic problems require periodontics specialists to take a more meticulous approach. If necessary, the number of sessions may be increased, and until infection control is achieved, the schedule for implant surgery related to bone should be postponed, ensuring medical principles are adhered to.
How Does Tobacco Use Affect Gum Healing and the Surgical Timeline?
One of the most misleading physiological situations encountered in clinics is the inflammation of the gums in smokers. In a healthy individual, gum tissues bleed in response to plaque buildup. However, due to the vasoconstrictive effect of nicotine, a smoker’s gums may be inflamed yet not bleed. Even if the patient believes their oral health is good, bacteria continue to erode the bone deep within the gum tissue.
After periodontal treatments, the formation of new capillaries (angiogenesis) and collagen synthesis by cells is necessary for the area to heal. When carbon monoxide mixes with the blood, it replaces oxygen. Cells that lack oxygen may take weeks to repair the tissue. To accurately assess tissue stability, oral surgeons prefer to keep the waiting period for gum treatment longer in heavy tobacco users compared to standard patients.
How to Limit the Risk of Gum Inflammation (Peri-implantitis) After Surgery?
The most critical parameter determining the lifespan of titanium materials is the health of the surrounding gum tissue (mucosal tissue). The approach of “treatment completed” contradicts the principles of sustainable dental care. Just as the tartar present before surgery is cleaned, it is medically necessary to prevent the accumulation of plaques that may build up around the prosthesis in the years following the surgery without organizing.
- Mechanical Washing: In addition to just brushing, food particles that get under bridge prostheses should be washed out with pressurized oral hygiene to disrupt anaerobic (oxygen-free) environments.
- Professional Clinical Care: Removal of hard deposits returning to tartar should be done every six months in a clinical setting using special teflon or carbon instruments that do not scratch the titanium surface.
- Early Diagnosis: If even a slight bleeding is detected while brushing the gum tissue (bleeding is an alarm), one should consult a physician without delay to treat it within the mucosal limits before the inflammation reaches the bone.







