

Implant Clinic in Izmir
Tooth loss in human anatomy is not just an isolated condition that disrupts chewing mechanics; it presents a broad physiological picture that initiates progressive volume loss (resorption) in the jawbones, disturbs the alignment of neighboring teeth, and exposes the temporomandibular joint (TMJ) to asymmetric stress. Titanium root surgeries applied to compensate for these tissue deficiencies are among the leading modern medical procedures capable of establishing a high level of integration with the biological environment. Individuals researching the implant clinic in Izmir often tend to focus solely on the surgical aspect of the treatment; however, the process has an integrated multidisciplinary structure that includes radiological planning, soft tissue maintenance, biomechanical prosthesis design, and long-term clinical care.
What Medical Criteria Should Be Considered When Choosing an Implant Clinic in Izmir?
The infrastructure of medical organizations is a fundamental determinant regarding the predictability of surgeries to be performed. Intervening in the jawbone requires much more than a routine dental practice; it necessitates an advanced infection control chain. Sterilizing the hand instruments and surgical motors according to medical norms helps prevent potential bacterial complications in the wound area.
However, planning operations solely with two-dimensional panoramic films is considered an inadequate approach in contemporary medical technologies. Three-dimensional imaging systems are essential to map the millimeter thickness of bone tissue around the lips and tongue, the anatomical sagging rates of the sinus cavities, and the route followed by the mandibular nerve canal. Conducting the examination in a transparent and objective manner in a digital environment minimizes the unexpected anatomical factors that the physician may encounter during the operation.
How Do Artificial Roots Placed in the Jawbone Achieve Biological Compatibility?
Many metals placed inside the organism are perceived as foreign bodies by the immune system, surrounded by an inflammatory envelope, and show a tendency to be expelled. However, titanium instantly forms an oxide layer on its surface due to its nature. This titanium dioxide layer is perceived as neutral (non-reactive) by the body’s defense cells (T-lymphocytes), meaning it does not cause any allergic rejection reactions.
The healing process consists of consecutive biochemical stages. After the surgical procedure, blood fills the microscopic gap that forms between the titanium and the bone. This blood clot serves as a scaffold (matrix) to allow bone-forming cells to adhere to the area. Over time, calcium and phosphate ions sediment within this soft matrix, mineralizing (hardening) the tissue. While this physiological hardening in the lower jaw takes an average of two to three months, the organization of cells in the spongy structure of the upper jaw spans a time frame of four to six months.
How are Prosthetic Restoration Plans Carried Out at Avrupadent?
A common situation encountered in traditional dentistry is when the surgeon places a screw into the most suitable gap found in the bone, followed by the prosthodontist attempting to create a tooth suitable for this screw. However, this isolated working method can lead to the artificial root and the porcelain tooth meeting at different angles (out of axis), potentially transmitting chewing forces to the jawbone as a destructive moment (lever effect).
- Virtual Modeling: The three-dimensional jaw copy of the patient is transferred to digital software using intraoral optical scanners. The prosthodontist virtually places the missing teeth (crowns) in ideal sizes and positions.
- Surgical Mapping: The surgical team positions titanium screws in the bone based on tomography data to align with the exact mid-axis of the virtual porcelain teeth.
- Guide Plate Production: This plan, agreed upon by the physicians in the digital environment, is transformed into a physical surgical template using 3D printers. By using this template during the operation, millimetric openings are preserved, and clinical error margins are minimized.
What are the Physiological Changes in the Jawbone During Tooth Loss?
The human skeletal system is a dynamic tissue that maintains its form according to the weight placed on it. When natural tooth roots transmit the force generated while breaking down food to the jawbone, this pressure sends a signal to bone cells (osteoblasts) that says, “there is an active function here.” When a tooth is extracted, this signal is entirely cut off, and the organism begins to retrieve calcium from that region back into the bloodstream, initiating a volumetric shrinkage (atrophy) cycle.
| Time Frame | Clinical and Physiological Effects |
|---|---|
| First 6 – 12 Months | Horizontal resorption (narrowing) of up to 25% occurs in the thin (cortical) bone plates around the lips and cheeks. The gum tissue gets destroyed. |
| 1 – 3 Years | The natural teeth next to the gap will tilt into the void unsupported, while the tooth on the opposite side extends towards the gap due to gravity. |
| 3 Years and Beyond | The vertical height of the bone shortens. The nerve canal in the lower jaw approaches the surface, and air cavities (sinuses) in the upper jaw sag below; necessitating advanced surgical intervention. |
How Does the Surgical Process and Medical Protocols Work in Implant Surgery?
Although the clinical aspect of the operation is often perceived by patients as a highly traumatic act; contemporary jaw surgery procedures are carried out with a philosophy of tissue respect (minimal invasive). Since there are no nerve endings within the bone, local blockage applied only to the membrane surrounding the bone (periosteum) and the gum mucosa ensures that the procedure is experienced without significant pain by the patient.
The tools used by the surgeon during the opening of the socket are quite specific. Bone is a sensitive tissue that can die (necrosis) when exposed to high heat. Therefore, rotary instruments (drills) used when opening the socket are operated at very low speeds, and the heating of the area is restricted with sterile cooling liquids. The torque applied while placing the titanium screw into the socket prevents excessive pressure on the bone causing it to crack, while ensuring that the screw does not move from its place, keeping it within a medical balance (usually between 35-45 Ncm).
What Augmentation Procedures Are Planned When Bone Volume Is Insufficient?
To ensure that titanium materials function stably for many years, they require a minimum of 1.5 – 2 millimeters of healthy and vascularized bone wall around them. If the jawbone is as thin as a knife’s edge or has significantly shortened vertically, surgeons perform “tissue engineering” by drawing the body’s repair cells to that area using biomaterials.
The calcium phosphate-based bone powders (xenograft or alloplastic materials) serve as a structural scaffold for cells. The surface of these powders is covered with collagen membranes that block the entry of rapidly proliferating gum tissue cells. The body weaves capillaries into these inorganic powders through a months-long angiogenesis (vascularization) process, turning them into living human bone (consolidation). The new volume created provides a suitable biological foundation for the secure positioning of the titanium root.
How Is Tissue Sensitivity of Patients Controlled During and After Operations?
It is essential for a healthy anatomy to initiate the body’s “inflammation” (repair) cycle at every tissue where a surgical incision is made. In the first forty-eight hours after the procedure, blood flow accelerates to bring connective tissue cells to the area, and blood vessels expand. This cellular activity causes slight swelling (edema) on the face and a local squeezing sensation when the effect of anesthesia wears off.
To help patients better cope with this physiological process, it is recommended to intermittently apply cold (ice) compresses to the outside of the surgical area. Cold compresses constrict blood vessels (vasoconstriction), limiting fluid accumulation in the area. The prophylactic antibiotics prescribed by doctors minimize the risk of infection, while mouth rinses (chlorhexidine gargles) help prevent microbial load in the wound area where mechanical cleaning cannot be performed.
How to Choose Zirconium and Porcelain Prosthetics Applied on Titanium Materials?
In the absence of teeth, the function of the front teeth is to cut food, while the function of the back teeth is to grind it. When the masseter (jaw) muscles contract, the mechanical stress in the back areas is significantly higher compared to the front areas. Therefore, each region requires a different biophysical structure for prosthetic material.
- Zirconium (ZrO2): These are inorganic structures that do not contain metal, are white, and reflect light like natural enamel. Thanks to their porous surfaces, they limit bacterial plaque accumulation and do not cause metallic discoloration at the gum margin. They are quite suitable for aesthetic areas.
- Monolithic Zirconium: These are materials carved from a completely single block, without a porcelain coating. They are planned in the back areas for patients with dental grinding (bruxism) habits to eliminate the risk of porcelain chipping/breakage.
- Porcelains with Metal Infrastructure: They have a biocompatible metal framework in their inner part. Due to their high flexural resistance in long-bodied bridge designs, they are a medical option in functional areas where aesthetics is secondary.
How is the Biomechanical Distribution of Bridge Prostheses Adjusted in Multiple Tooth Gaps?
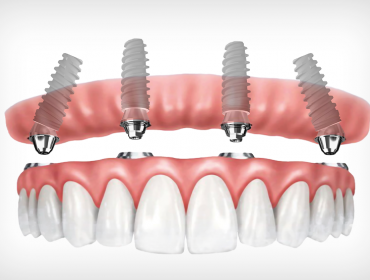
In cases of multiple deficiencies, unnecessarily drilling a high number of holes in the bone tissue can disrupt the vascularization of the bone, creating a groundwork for tissue death (necrosis). Two thick titanium materials have the mechanical strength to support the missing tooth gap between them. In traditional bridges, natural teeth are shaped, while in implant bridges, only artificial roots within the bone provide support, and no intervention is made on adjacent natural teeth.
According to physical rules, connecting two feet with a rigid (non-flexible) prosthesis restricts the chewing force from concentrating at a single point. When the patient bites, the force is distributed throughout the skeleton. However, in the designs of these bridges, the clinical consideration that physicians pay attention to is the shaping of the parts of the bridge (pontic) that remain suspended in the air so that they do not exert excessive pressure on the underlying gum mucosa and allow for cleaning access (in an egg shape or slightly touching).
What Medical Precautions are Taken During Surgical Procedures for Individuals with Systemic Diseases?
Oral surgery is not an isolated procedure from the body’s overall systemic circulation. The formation of new capillaries (angiogenesis) around titanium material and collagen synthesis by cells necessitate the performance of the patient’s circulatory and connective systems. Especially in uncontrolled diabetes cases, high glucose damages cell walls, slowing down tissue nutrition; this situation can disrupt the process of osseointegration.
In clinical practices located in Izmir, an expanded blood count examination is conducted for individuals in this risk group. The amount of vasoconstrictor (such as adrenaline) used during anesthesia is modified by the physician, as procedural stress may affect the pulse of hypertension patients. Patients who have completed their medical preparation and whose diseases are managed within medical limits can benefit from these restorative surgeries, just like ordinary individuals; systemic disease is not an obstacle but a parameter that requires additional medical attention.
How Does Tobacco Use Affect the Healing Timeline in Jawbone Surgeries?
The element most needed for the closure of a wound or bone incision is oxygen. The carbon monoxide that enters the bloodstream with tobacco smoke replaces the oxygen in the blood, giving cells a false sense of fullness. Fibroblast (wound-healing) and osteoblast (bone-forming) cells cannot sufficiently heal the tissue in this environment where they are deprived of oxygen.
Especially in patients where bone graft material is applied, the ability of the added biomaterial to transform into a living structure entirely depends on the formation of new blood vessels that will extend to the area. Continuing tobacco use not only prolongs the healing timeline by months but also leads to the weakening of the gum around the titanium root (mucosal layer), leaving the door open for “peri-implantitis” (bone resorption) in the coming years.
How Are Long-Term Oral Care and Clinical Maintenance Periods Organized in Izmir?
The presence of biomechanical systems in the oral environment cannot be sustained with the notion of “made and finished.” Although inorganic structures like zirconium or porcelain do not decay, the surrounding gums and bone are biologically sensitive tissues vulnerable to bacterial attacks. If the patient neglects oral hygiene, the bacterial plaque that accumulates in the neck area between the prosthesis and the gum will harden into tartar (calculus) within twenty-four hours.
Tartar, by attracting more bacteria to the area, initiates an inflammatory reaction and compromises the bone tissue that holds the titanium root. Clinical maintenance sessions conducted in equipped institutions in Izmir aim to limit these cellular damages before they begin. Doctors remove microbial residues with non-abrasive Teflon or carbon-tipped instruments. Simultaneously, occlusal contacts, which can change over the years due to the wear of natural teeth, are tested with articulation papers, and the excessive loads on the prosthesis are adjusted to provide medical support against mechanical stress.







