

What to Do If the Implant Screw Breaks?
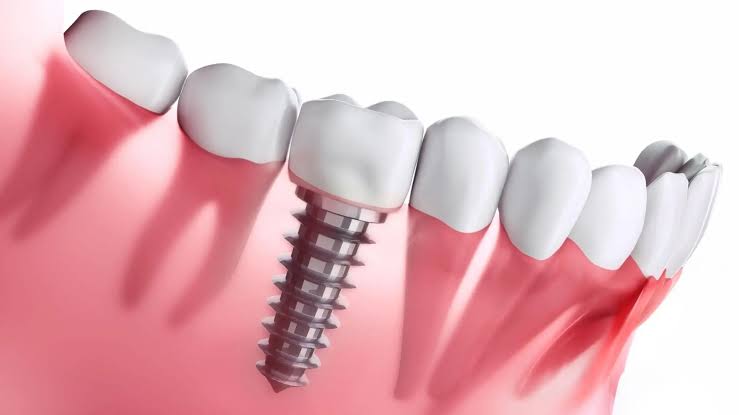
Titanium artificial root systems used to compensate for missing teeth, despite being designed to withstand the highest chewing pressures produced in the human body, are exposed to constantly repeating micro and macro mechanical stresses throughout their usage lifespan spanning decades. These systems generally consist of two main parts (the fixture embedded in the bone and the abutment/connection screw carrying the prosthesis). Due to asymmetry of the temporomandibular joint (TMJ) movements, parafunctional habits such as teeth grinding (bruxism), or longstanding metal fatigue, breakages may occasionally occur in the internal connection screws of these artificial systems.
What to Do If the Implant Screw Breaks and What Should the Initial Medical Approach Be?
The fracture event occurring in a biomechanical system may seem concerning from the patients’ perspective, but it is considered a manageable complication in dental clinical practices. The fractured piece is generally the thin “abutment screw” that connects the porcelain prosthesis to the main body, rather than the main body itself, which has already fused into the jawbone. This screw serves as a safeguard that absorbs external excessive pressure and protects the underlying bone structure. When the safeguard fails (when the screw breaks), the porcelain tooth may shift or fall into the oral cavity.
In this physiological scenario, the clinician’s clinical priority is to ensure that the main structure in the jawbone does not deform the inner screw pathways (its grooves). The broken piece usually remains tightly lodged in the inner tunnel of the artificial root. During the intervention, local anesthesia is used to control tissue sensitivity, and the fracture line is visualized with the help of surgical microscopes (or magnifying loupes). Once the broken piece is successfully removed from its socket, the prosthesis is reattached with a brand-new healthy screw either within the same session or after a new measuring phase, and biting function is restored to medical standards.
What Physiological or Biomechanical Reasons Can Cause a Titanium Connection Screw to Break?
The human jaw muscles (especially the masseter muscle) are among the strongest muscle groups in the body and exert forces equivalent to kilograms on the jaw bones during chewing. Natural teeth absorb these high forces by flexing due to the flexible periodontal connective tissue fibers surrounding them. However, titanium artificial roots do not have such shock-absorbing properties because they fuse directly to the bone (ankylosis). All force concentrates at the neck region of the connecting screw.
| Risk Faktörü | Mekanik ve Fizyolojik Reaksiyonu |
|---|---|
| Oklüzal Erken Temas (Yüksek Kapanış) | Even at a micron level, early contact between a porcelain tooth and the opposing tooth causes all jaw pressure to focus on that screw, leading to metal fracture. |
| Metal Yorgunluğu (Fatigue) | Repeated chewing cycles millions of times over the years can create micro-cracks in the titanium alloy’s molecular structure, eventually leading to breakage. |
| Hatalı Tork Değeri Uygulanması | When attaching a prosthesis, excessively tightening the screw well over (excessive) or well below (loose) medical standards exceeds the limits of mechanical tolerance. |
| Pasif Uyumsuzluk (Non-passive Fit) | Metal casting errors between the legs of bridge prostheses create a constant stress on the screws, facilitating the failure of the structure. |
What Are the Clinical Differences Between Fracture of the Main Fixture Within the Jawbone and Fracture of the Abutment Screw?
In dentistry, the management of biomechanical complications varies according to the anatomical or equipment level at which the damage occurs. The expression “My implant is broken” is often a common misconception used by patients concerning the porcelain crown on top. In a significant majority of cases, the broken piece is the intermediary screw, a replaceable medical spare part. Doctors remove this screw, which remains in the internal abutment, using specialized protocols to continue the patient’s treatment from where it was left off.
Much rarer main body (fixture) fractures mostly occur due to intensive bone resorption (peri-implantitis) in the neck region (at the crest level), resulting in the titanium root losing its support and breaking from the thin neck part. When the main body is broken, it is mechanically impossible to construct a new tooth on the system. In this clinical scenario, the surgeon removes the broken body with specialized trepan drill bits that cause minimal damage to the bone. The created bone defect is filled with biomaterials (bone powder) and left to heal.
What Should Individuals Carrying the Suspicion of Implant Screw Breakage Pay Attention to Before Clinical Application?
Metal or porcelain pieces that become loose within the mouth following a breakage in a biomechanical system pose a hidden physical risk to the patient’s vital functions. Particularly, swallowing a prosthetic piece that has come loose during sleep or while eating can lead to gastrointestinal (stomach-intestinal) or respiratory complications. Therefore, it is essential to take the medical process seriously even at the slightest movement of the tooth or when a metallic clicking sound is heard.
If the porcelain crown has completely come off, the patient should bring this piece to the clinic stored in a clean tissue or container. The exposed internal socket of the titanium root can transform into an open cavity, allowing bacteria and food particles to accumulate. The patient should not attempt to clean this socket with a toothpick or sharp objects; as this mechanical intervention may cause scratches to the internal grooves and lead to the inability for a new screw to hold. Instead, the microbial load in the area should be limited by performing passive rinsing with chlorhexidine-based chemical gargles.
What Surgical Protocols Are Followed in the Procedure of Removing the Broken Piece from the Jawbone?
The development of medical equipment has greatly facilitated the management of complications at microscopic levels. The broken screw fragment is usually found tightly lodged several millimeters deep within the main body. It is often impossible for the physician to access this piece with standard tools. The most critical point of the removal protocol is to prevent drawing the outlines of the titanium inner walls of the main fixture device.
- Visualization (Ensuring Visibility): The position of the break is clarified using clinical light sources and magnifying loupes. The inner socket is washed with sterile physiological serum to eliminate blood or food debris.
- Ultrasonic Vibration: Very fine-tipped ultrasonic tools are applied to the top of the broken screw. This tip vibrates thousands of times per second, breaking the stress adhered to the screw between its threads at the micron level.
- Reverse Torque: Using specially designed extraction drills (extraction kits) that operate in the opposite direction of the clock, the screw is rotated backwards in its socket and taken out with the help of a forceps (presel).
How is a Multidisciplinary Approach Displayed in Broken Screw Cases at Avrupadent Organizations Serving in the İzmir Region?
When a biomechanical complication occurs, it is a medical fact that the issue is not merely about removing the broken piece. If the root cause of why the screw broke is not identified, the new screw will also face the same fate within months. The foundation of a multidisciplinary clinical approach is to identify and eliminate the anatomical or mechanical deficiencies that caused the problem.
Prosthodontists examine the patient’s jaw closure (occlusion) after the broken piece is removed using articulation papers or digital occlusal analysis devices. If a point of severe impact from the opposing tooth is detected on the porcelain crown, that area is adjusted millimetrically to distribute force. If an inadequate support structure is in question, the prosthesis is sent back to the lab to reconstruct the support framework with thicker metal or monolithic zirconium.
What Are the Biomechanical Effects of Occlusal Forces on Titanium Materials?
The anatomy of the jaw generates a massive mechanical force during chewing, ranging from 50 to 100 kilograms. The perfection of natural anatomy lies in the ability of the shock-absorber-like fibers attached to the jawbone to dissipate this force. Artificial root applications, however, are essentially structures that have been welded to the bone cells (ankylosis); there is absolutely no elasticity allowance within the material inside the bone, even a quarter of a millimeter.
If the titanium root is placed at a perpendicular angle (parallel) to the jawbone and the force comes from above downwards (vertically), the system transfers this load effortlessly to the bone. However, if the material is placed incorrectly due to anatomical constraints or if a force is applied laterally (horizontal/shear) from the outside edge of the prosthesis, this force creates a lever effect. The lever force focuses on the inner screw, which is the most delicate and connected point of the system. Over time, the screw weakens and breaks in a manner similar to the physiology of a wire being constantly bent at the same point.
Does Bruxism (Teeth Grinding) Cause Mechanical Fatigue in Prosthetic Restorations?
During the day, our teeth only come into contact for a few minutes while eating, and when the chewing function is finished, the jaw muscles return to a resting position. However, in bruxism, an individual clenches their teeth together throughout the night, shifting their jaw to the left and right. This means that horizontal forces (shearing) are applied continuously on the artificial roots for hours.
Individuals with a habit of teeth grinding have overdeveloped and strengthened jaw muscles (masseter muscles). Titanium systems placed in the jawbone work to resist this horizontal pressure while micro-fractures begin to occur between the threads (denticles) of the connecting screws. This fracture initially leads to the loosening of the screw (the patient feeling a play in the tooth). If chewing or teeth grinding continues with a loosened screw, the screw eventually loses its breaking tolerance and snaps. To prevent this complication, doctors prescribe a hard acrylic protective “occlusal splint” (night guard) for bruxism patients to wear while sleeping.
Can a new surgical procedure be planned in the same area after the removal of broken material?
In case of fracture of the main material, patients often carry the concern that “a tooth cannot be placed there again” because a destruction has occurred in that region. However, human bone has an excellent capacity to remodel itself (remodeling) when appropriate medical conditions are met. When the surgeon removes the fractured piece with micro tools (trepan drills) that cause minimal damage to the surrounding bone tissue, a cylindrical void remains behind.
The inside of this void is filled with inorganic calcium particles that support the blood clot and repair cells. It is expected that through the body’s angiogenesis (vascularization) activity, the area will turn into hard human bone within months. When moving to the second surgical phase, the physician usually selects a material that is at least one millimeter wider than the extracted material to ensure that the newly opened cavity tightly adheres to the living and healthy bone walls (primary stability).
What Are the Biophysical Factors Affecting the Durability of Titanium Connection Parts?
In mechanically joined systems where parts are screwed together, the compatibility of the components should be at the micron (one thousandth of a millimeter) level. The metal frame or zirconium base to be constructed on top should sit perfectly on the titanium root without any pushing or stressing force (passive fit). If the structure is somewhat tense and the doctor attempts to close this gap by tightening the screw, the screw will be under tensile stress from the outset and will enter a fracture phase even before chewing begins in the mouth.
| Biophysical Factors | Clinical Function and Effect |
|---|---|
| Use of Torque Wrench | Screws are tightened with specific dynamometric wrenches at forces determined by manufacturing companies in Newton/cm (e.g., 35 Ncm). Excessive tightening prepares the ground for the screw to elongate and break. |
| Crown – Root Ratio | If the root inside the bone is very short and the porcelain tooth on it is very long; the leverage effect increases. The load reaching the peak of the porcelain creates a moment that can break the screw at the bottom. |
| Connection Geometry | The internal design of titanium roots (inner hexagon, Morse taper, etc.) ensures that the force is distributed to the walls of the root rather than the screw, limiting the stress on the screw. |
How is a Medical Roadmap Drawn for Material Breakages Experienced by Individuals in the Advanced Age Group?
Physiological changes associated with aging somewhat slow down the tissue repair rate (fibroblast and osteoblast activity). A significant number of older individuals use various medical drugs due to cardiovascular (heart-vessel) or endocrine (diabetes, osteoporosis) disorders. In these patients, when the primary material fracture occurs, making a large surgical incision in the jawbone can risk cellular healing.
Medical boards limit the surgical radicalism when managing these complications in elderly patients. If removing the fragment would cause a significant loss in the bone, sometimes the fractured piece can be left buried below the bone level and covered with gum tissue (leaving it in sleep), and prosthetic support can be obtained from another area. If a new surgical plan is to be made, the medications used by the patient to slow the bone degradation (bisphosphonates) and anticoagulants are discussed with the relevant medical doctors, and the operation schedule is carried out within the body’s tolerance limits.
How Do Regular Clinical Treatment Appointments Function in Preventing Possible Mechanical Complications?
The stability of artificial systems integrated into the jawbone for decades is possible not with the notion of “it was made and done,” but through continuous clinical observation. While people’s natural teeth gradually wear down over the years as they chew, zirconium or porcelain materials do not wear down. This situation leads to a deterioration of the mechanical compatibility over the years and causes disproportionate loads (early contacts) on the prosthetic structure.
Routine doctor visits are check-up sessions that detect these imbalances before material fatigue occurs. The doctor conducts a chewing simulation by placing colored thin papers on the tooth. In areas with excessive pressure, porcelain is milled down millimetrically and redistributed. If the patient feels a slight clicking or stretching in the prosthesis, the doctor will open the screw seat and replace the stretched or fatigued interim screw (before it breaks) with a new one. This protective dental principle serves as the only scientific shield that preserves the structural integrity of the system.







